in pictures and a few words
What it is and why it matters
Roxadustat is a tablet for anaemia in people with kidney disease. It helps the body make its own hormone that starts blood production.
- For adults with kidney disease — both on dialysis (blood cleaning by a machine) and before it
- A tablet instead of hormone injections
- No need to keep it cold
Why kidney disease brings anaemia
The kidneys are not just a filter. They make a hormone that tells the bone marrow to produce red blood cells.
- When the kidneys are ill, this hormone runs low
- Haemoglobin falls — this is how a blood test shows anaemia
- Hence weakness, breathlessness, and cold and exertion are harder to bear
Why iron alone is not enough
Blood needs material — iron — and a command — the kidney hormone. With kidney disease, the main trouble is usually the missing command.
- There may be enough iron, yet haemoglobin still does not rise
- An iron shortage is also corrected, but iron alone will not cure this anaemia
How the tablet works
Every cell has an oxygen sensor. The tablet makes the cell think oxygen is low — as if the person had climbed a mountain.
- In the mountains, the body boosts blood production by itself
- The tablet switches on the same thing: the body makes its own hormone instead of getting it by injection
- Scientists received a Nobel Prize for discovering this sensor
Tested in people
The tablet was compared with the standard hormone injection in people on dialysis, and with a dummy pill in those not yet on dialysis.
- On dialysis, haemoglobin rose no worse than with the injection
- Before dialysis, haemoglobin rose clearly, while on the dummy pill it kept falling
- A large review did not find more heart problems with it than with injections
Tested in people. Tested in people: studies in people with kidney disease — both on dialysis and before it.
A lock on the iron pantry
The body has a lock hormone: it keeps iron locked away in the stores. The tablet opens this lock a little.
- With kidney disease, this hormone is usually high, and iron stays “under lock”
- Blood tests show iron metabolism shifting in a good direction
Cholesterol goes down too
The same mechanism lowers blood cholesterol. This is a side effect of the tablet.
- It is used to treat anaemia; cholesterol has its own medicines
How it is taken
The tablet is taken three times a week. No injections, no trips for them and no cold storage.
- The doctor sets the dose by haemoglobin and adjusts it during treatment
- The goal is not “the higher, the better”: haemoglobin has upper and lower limits
Who should see a doctor first
This is a prescription medicine. A kidney doctor — a nephrologist — prescribes it after tests for iron, potassium and blood acidity and a check of the heart and blood vessels.
- Potassium may rise — this is dangerous for heart rhythm; tests follow the nephrologist’s plan
- The blood may turn more acidic — this also shows on routine tests
- The tablet is not approved in every country — your nephrologist will tell you what is available
Important. Do not take it on your own: the nephrologist sets the dose and checks the tests.
In one sentence
With kidney disease, the tablet helps the body make its own blood hormone and raises haemoglobin — on dialysis no worse than an injection; a nephrologist prescribes it and watches the tests.
Key points
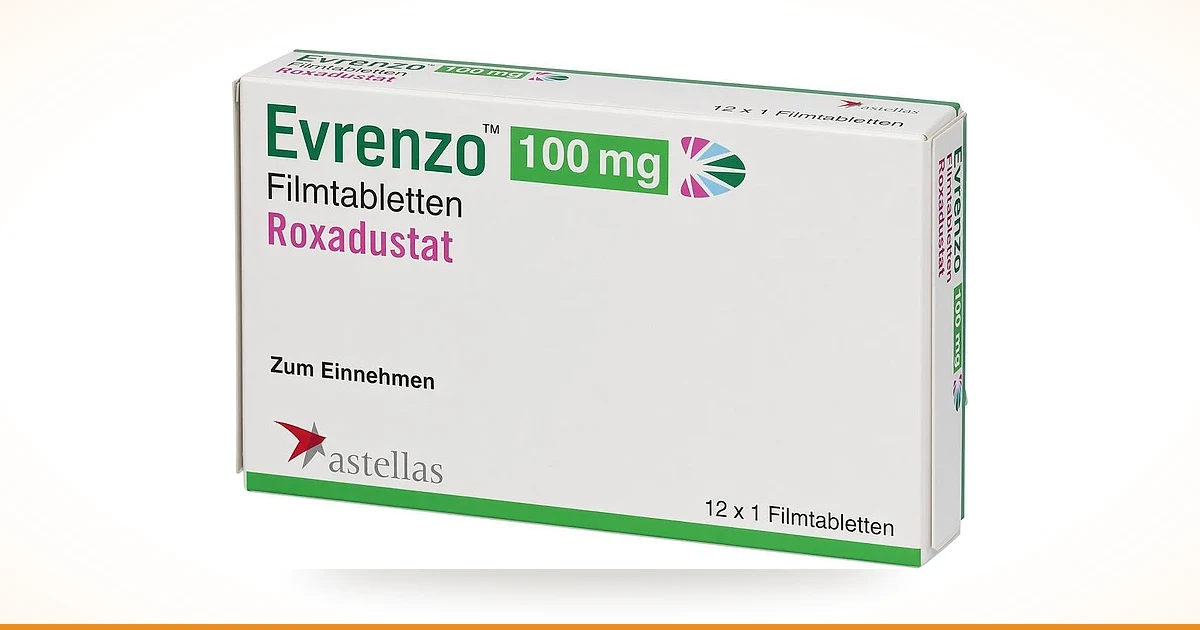
Roxadustat (brand name Evrenzo, Astellas) is a tablet for anaemia of chronic kidney disease (CKD): rather than replacing the hormone by injection, it makes the body produce its own erythropoietin.
| Situation | How it helps | What human studies showed |
|---|---|---|
| Anaemia of CKD in patients on dialysis | raises haemoglobin: the body produces its own erythropoietin instead of receiving the hormone by injection | non-inferior to injected epoetin alfa (305 patients) [1]; in phase 3 with 2,133 patients the haemoglobin rise was 7.7 g/L (0.77 g/dL) versus 6.8 g/L (0.68 g/dL) [2] |
| Anaemia of CKD before dialysis | raises haemoglobin | 154 patients, 8 weeks: +19 g/L (+1.9 g/dL) versus −4 g/L (−0.4 g/dL) on placebo [3] |
| Iron handling | lowers hepcidin, the hormone that keeps iron locked in storage | meta-analysis of 16 randomised trials: lower hepcidin, higher transferrin and total iron-binding capacity [4] |
| Treatment convenience | taken orally three times a week, with no injections and no cold chain | — |
How it helps
Why haemoglobin falls in kidney disease
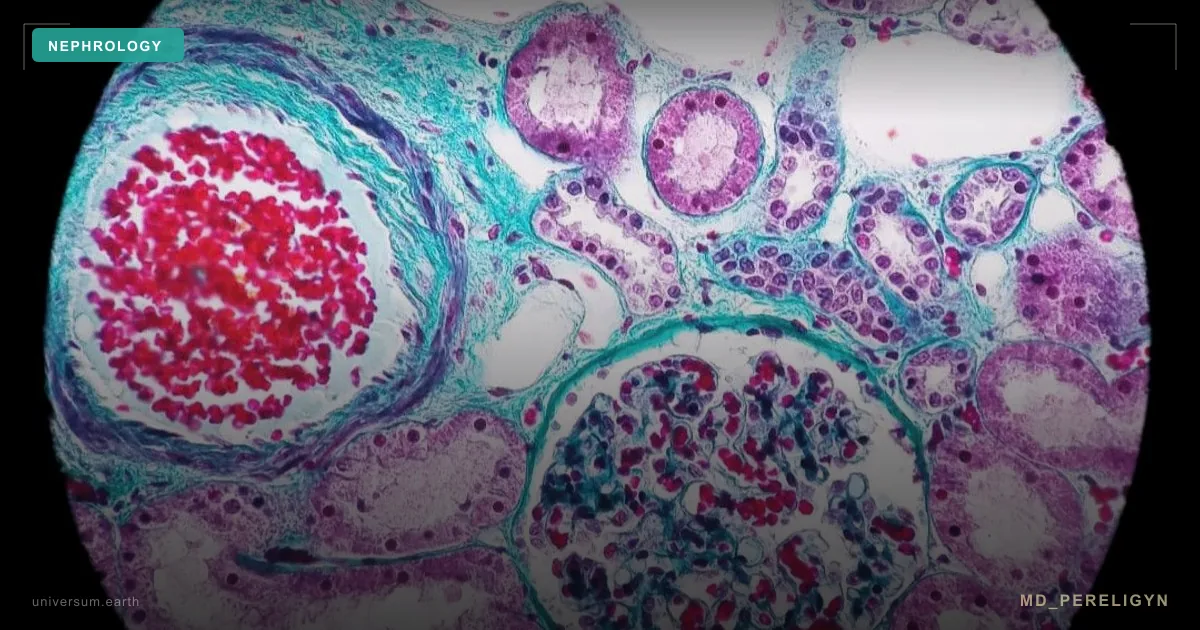
The kidney is not only a filter. Its tissue contains specialised cells that continuously measure how much oxygen the blood delivers. When oxygen runs low they release erythropoietin, the bone marrow receives the order and steps up red cell production. More red cells, more oxygen carried — the loop closes.
In chronic kidney disease those cells are lost along with the rest of the tissue. The sensor remains; the instruction does not. Haemoglobin falls, and the patient feels weak, breathless on ordinary exertion, cold-intolerant and less able to work physically. Anaemia in CKD is not cosmetic: it degrades quality of life and is associated with worse outcomes.
How this differs from iron deficiency anaemia. The distinction is fundamental and constantly blurred:
| Iron deficiency anaemia | Anaemia of CKD | |
|---|---|---|
| What is missing | Raw material — iron | The instruction — erythropoietin |
| What the labs show | Low ferritin, low transferrin saturation | Ferritin may be normal or high; kidney function reduced |
| How it is treated | Iron repletion | Stimulating erythropoiesis; iron is supportive |
| What happens with iron alone | Haemoglobin rises | Haemoglobin does not rise — the instruction is still absent |
In practice the two often coexist: iron deficiency is common in CKD and does need correcting — but as a precondition, not as the solution. On reading iron stores correctly, see the ferritin and hair loss guide: the same logic applies to the labs.
How a cell senses oxygen
For thirty years the answer to anaemia of CKD was injecting synthetic erythropoietin. Roxadustat works on a fundamentally different principle — it fools the cellular oxygen sensor. That sensor was deciphered by William Kaelin, Sir Peter Ratcliffe and Gregg Semenza, who received the 2019 Nobel Prize in Physiology or Medicine for the work.
Every cell contains a protein called HIF — hypoxia-inducible factor. It acts as the switch for the "oxygen is scarce" programme, turning on genes that aid survival under low oxygen, including the erythropoietin gene and genes governing iron handling and vessel growth.
At normal oxygen levels HIF is essentially absent, and here is why. Enzymes called prolyl hydroxylases use oxygen as a reagent: they tag HIF, and the tagged protein is immediately sent for disposal. While oxygen is sufficient, the enzymes work, HIF is destroyed within minutes and the programme stays off.
When oxygen becomes scarce — at altitude, after blood loss, in anaemia — the enzymes run out of their reagent. They stall, HIF stops being destroyed, accumulates and switches on adaptation: the kidney and liver produce more erythropoietin.
Two practical consequences follow. First, the body's own physiological system does the work rather than an externally injected hormone, and erythropoietin concentrations stay closer to physiological than with injections. Second, HIF switches on a programme rather than a single gene — which is why the drug has effects beyond haemoglobin, covered below.
What the trials showed
- On dialysis. The pivotal trial (n=305, New England Journal of Medicine, 2019) compared roxadustat with injected epoetin alfa in patients on long-term dialysis: the drug was non-inferior to standard therapy — a comparable haemoglobin rise with an oral drug instead of injections [1].
- On dialysis, phase 3. A larger comparison against epoetin alfa (n=2,133, Journal of the American Society of Nephrology, 2022): mean haemoglobin increase 7.7 g/L (0.77 g/dL) versus 6.8 g/L (0.68 g/dL) [2].
- Before dialysis. Compared with placebo (n=154, New England Journal of Medicine, 2019): haemoglobin change +19 g/L (+1.9 g/dL) versus −4 g/L (−0.4 g/dL) on placebo over 8 weeks [3].
On dialysis the value of the drug lies in the route of administration: a tablet instead of injections. Before dialysis the difference is large and clinically tangible — on placebo haemoglobin kept falling, on the drug it rose appreciably.
What happens to iron
HIF governs iron handling as well as erythropoietin, and this is one of the most discussed aspects of the drug.
The key player is hepcidin, a hormone that acts as a gate: when it is high, iron stays locked in storage and does not reach the circulation. In chronic inflammation — and CKD is an inflammatory state — hepcidin is elevated and iron sits in the pantry under lock.
A meta-analysis of 16 randomised trials shows that roxadustat lowers hepcidin and raises transferrin and total iron-binding capacity [4]. The gate opens somewhat and iron transport increases: iron handling shifts favourably, as confirmed on laboratory measures.
Cholesterol: a by-product of the mechanism
The HIF programme also touches hepatic cholesterol synthesis. In the non-dialysis trial total cholesterol fell by 1.05 mmol/L (40.6 mg/dL) versus 0.20 mmol/L (7.7 mg/dL) on placebo [3], and a reduction in low-density lipoprotein (LDL) cholesterol appears in the meta-analysis too [4].
Who this is for
- adults with confirmed chronic kidney disease and anaemia, on dialysis or before it;
- those for whom erythropoietin injections are inconvenient, poorly tolerated or logistically out of reach;
- those whose anaemia persists despite repleted iron stores — that is, when the missing element really is the instruction rather than the material.
How to take it
The dose is set by the clinician according to haemoglobin and adjusted over time — the haemoglobin target in CKD is bounded on both sides, and "the higher the better" does not apply.
Where the drug is approved
| Region | Status |
|---|---|
| Japan | Approved |
| China | Approved |
| European Union | Approved as Evrenzo (Astellas) |
| United States | FDA declined approval citing safety concerns |
In the US two other HIF prolyl hydroxylase inhibitors are approved — daprodustat (2023) and vadadustat (2024) — both for dialysis patients only. Availability depends on the country: a nephrologist knows what is registered where you live and what can actually be obtained.
Who should see a doctor first
Roxadustat is a prescription drug. It is started and monitored by a nephrologist after assessing iron, potassium, acid-base status and cardiovascular risk; it is not for self-administration.
Erythropoiesis-stimulating agents have a complicated cardiovascular safety history. A meta-analysis of 15 studies covering 143,065 patients (Frontiers in Pharmacology, 2024) found no increase in cardiovascular events compared with erythropoiesis-stimulating agents [6].
Two findings did occur more often than on placebo and should be known in advance:
| Finding | Why it matters in CKD | What to do |
|---|---|---|
| Hyperkalaemia — raised blood potassium | Potassium is already cleared less efficiently in kidney disease, and high potassium threatens cardiac rhythm | Monitor potassium on the schedule set by the nephrologist |
| Metabolic acidosis — acidification of the blood | The failing kidney is less able to maintain acid-base balance | Monitor bicarbonate and acid-base status |
Both are tracked with routine tests and both belong to standard nephrology follow-up — what matters is that the clinician knows to look.
Bottom line
- Anaemia in CKD is a missing instruction, not missing material: the kidney fails to produce erythropoietin, and iron alone will not fix it.
- Roxadustat switches on endogenous hormone production by blocking the enzymes that destroy HIF — the applied continuation of work awarded the 2019 Nobel Prize.
- Efficacy is established: non-inferior to epoetin alfa on dialysis, clearly superior to placebo before dialysis.
- Iron handling shifts favourably — lower hepcidin, higher transferrin.
- Cholesterol falls as a by-product of the mechanism.
- No excess cardiovascular risk was found across 143,065 patients; potassium and acid-base status are tracked with routine tests.
- Oral dosing three times a week instead of injections.
- Approved in Japan, China and the EU; not in the US (the FDA declined approval citing safety concerns), where daprodustat and vadadustat from the same class serve dialysis patients.
References
1. Chen N, et al. Roxadustat treatment for anemia in patients undergoing long-term dialysis. N Engl J Med. 2019;381(11):1011–1022. PMID 31340116
2. Fishbane S, et al. Roxadustat versus epoetin alfa for treating anemia in patients with chronic kidney disease on dialysis: results from the randomized phase 3 ROCKIES study. J Am Soc Nephrol. 2022;33(4):850–866. PMID 35361724
3. Chen N, et al. Roxadustat for anemia in patients with kidney disease not receiving dialysis. N Engl J Med. 2019;381(11):1001–1010. PMID 31340089
4. Lei J, et al. Efficacy and safety of roxadustat in patients with chronic kidney disease: an updated meta-analysis of randomized controlled trials. Biomed Res Int. 2022. PMID 36420092
5. Wu H, et al. Roxadustat and oral iron absorption in Chinese patients with anemia of chronic kidney disease. Adv Ther. 2024;41(3):1168–1183. PMID 38280066
6. Li X, et al. Assessment of the safety of roxadustat for cardiovascular events in chronic kidney disease-related anemia: a systematic review and meta-analysis. Front Pharmacol. 2024. PMID 38962312
7. The Nobel Prize in Physiology or Medicine 2019 — William G. Kaelin Jr., Sir Peter J. Ratcliffe, Gregg L. Semenza, "for their discoveries of how cells sense and adapt to oxygen availability". Nobel Assembly at Karolinska Institutet.
Caveats
- "Non-inferior" is not "superior". On dialysis this means efficacy comparable to epoetin alfa, not superiority.
- Iron absorption. The tempting conclusion — "therefore iron from food and tablets is absorbed better" — sounds convincing but is not directly evidenced: the study that specifically tested oral iron absorption on roxadustat enrolled just 25 patients and lacked the power to confirm it [5]. The clinical significance of the laboratory shift in iron handling remains an open question.
- Cholesterol. The drug was not studied as a lipid therapy, the effect of this reduction on cardiovascular outcomes has not been shown, and for cholesterol there are agents with proven outcome benefit. It is a feature of the mechanism, not an indication.
- United States. The FDA declined approval citing safety concerns: the regulator accepted the class while rejecting this particular molecule.
- What roxadustat is not. It is not an "energy" remedy, not a substitute for iron in ordinary iron deficiency, and not a cholesterol drug.
For information only; prescribing and the treatment schedule are decided by a nephrologist.
Key facts
- Anaemia of chronic kidney disease is primarily a deficit of erythropoietin, not of iron: the damaged kidney stops producing the hormone that instructs the bone marrow to make red cells. Iron deficiency is often present too, but iron alone will not raise haemoglobin.
- Roxadustat (brand name Evrenzo, Astellas) is a HIF prolyl hydroxylase inhibitor: it prevents the destruction of hypoxia-inducible factor, so the cell behaves as though oxygen were scarce and switches on its own erythropoietin synthesis. The cellular oxygen-sensing mechanism was uncovered by Kaelin, Ratcliffe and Semenza, who received the 2019 Nobel Prize in Physiology or Medicine for it.
- On dialysis, roxadustat was non-inferior to injected epoetin alfa: a 305-patient trial (New England Journal of Medicine, 2019) showed a comparable haemoglobin rise with an oral drug instead of injections, and in a phase 3 trial of 2,133 dialysis patients the mean increase was 7.7 g/L (0.77 g/dL) versus 6.8 g/L (0.68 g/dL) with epoetin alfa.
- In patients not yet on dialysis the difference against placebo was substantial: +19 g/L (+1.9 g/dL) versus −4 g/L (−0.4 g/dL) over 8 weeks (n=154). The drug also lowers hepcidin — the hormone that blocks the release of iron from storage — and raises transferrin and total iron-binding capacity (meta-analysis of 16 randomised trials).
- Dosing is oral, three times a week, with no injections and no cold chain. A meta-analysis of 15 studies covering 143,065 patients found no increase in cardiovascular events compared with erythropoiesis-stimulating agents. Hyperkalaemia and metabolic acidosis occurred more often than on placebo, so potassium and acid-base status are tracked with routine tests. The drug is approved in Japan, China and the European Union (Evrenzo); in the US the FDA declined approval citing safety concerns.