Key points
Why the thyroid needs iodine
The thyroid builds iodine into its hormones, thyroxine (T4) and triiodothyronine (T3). Without iodine it is overworked: the Burgerstein handbook describes goitre, nodules, cysts and areas that work on their own (Burgerstein, Handbuch Nährstoffe 2015, p. 128).
In Hashimoto’s thyroiditis (autoimmune thyroiditis), the immune system attacks the thyroid. The main marker of the disease is thyroid peroxidase antibodies (TPO antibodies); more on them in the article Anti-TPO: the main marker of autoimmune thyroiditis. Thyroid function is assessed by thyroid-stimulating hormone (TSH) from the pituitary gland: when thyroid hormones are lacking, TSH rises.
How much iodine is needed per day
Where iodine comes from
The main source is food: products with added iodine, such as salt, dairy products and bread, and, among natural sources, seafood (Leung AM Nat Rev Endocrinol 2014. PMID 24342882[1]).
Seaweed is a special case: it contains a lot of iodine, and the amount is unpredictable. In 12 species of edible seaweed it ranged from 16 µg per gram in nori to 8165 µg per gram in one sample of kelp salt-substitute granules (Teas J Thyroid 2004. PMID 15588380[7]).
More iodine: what the data show
In Denmark, 4–5 years after cautious mandatory salt iodisation, even though intake was raised only to the lower end of the normal range, TPO antibodies were found in 23.8% of people in the general population versus 14.3% before it, and thyroglobulin antibodies (Tg antibodies) in 19.9% versus 13.7%. The rise was more noticeable in young women and was mostly due to low antibody levels (Pedersen IB Clin Endocrinol 2011. PMID 21521277[9]).
A usual dose or supplements
Supplements, and kelp in particular, can give a dose several times above the norm. The European tolerable upper intake level for adults is 600 µg a day, and 26 seaweed products in the UK, calculated per serving, could exceed it (Bouga M Foods 2015. PMID 28231201[11]). The US upper level is 1100 µg a day for adults, and some Asian seaweed dishes can also exceed it (Teas J Thyroid 2004. PMID 15588380[7]). The upper level is a ceiling, not a target; in Hashimoto’s, sensitivity to iodine may be higher (Leung AM Nat Rev Endocrinol 2014. PMID 24342882[1]), so a supplement on top of food is discussed with a doctor.
Pregnancy with Hashimoto’s
The need for iodine rises in pregnancy in all women (Zimmermann MB Am J Clin Nutr 2009. PMID 19088150[3]), and with Hashimoto’s it is important not to overdo it: the fetus and the newborn are also sensitive to excess iodine (Leung AM Nat Rev Endocrinol 2014. PMID 24342882[1]). Whether a supplement is needed, at what dose and how often to check TSH is decided together with the doctor. TSH targets in pregnancy are covered in the article TSH norms in pregnancy.
What the studies showed
| What was studied | Who or what | Result |
|---|---|---|
| Iodine intake and thyroid disease, China, 5 years, 2006 | 3018 people in three regions | Subclinical hypothyroidism: 0.2% with mild deficiency, 2.6% above the norm, 2.9% with excess |
| Before and after salt iodisation, Denmark, 2011 | 4649 and 3570 people | TPO antibodies: 14.3% → 23.8%; Tg antibodies: 13.7% → 19.9% |
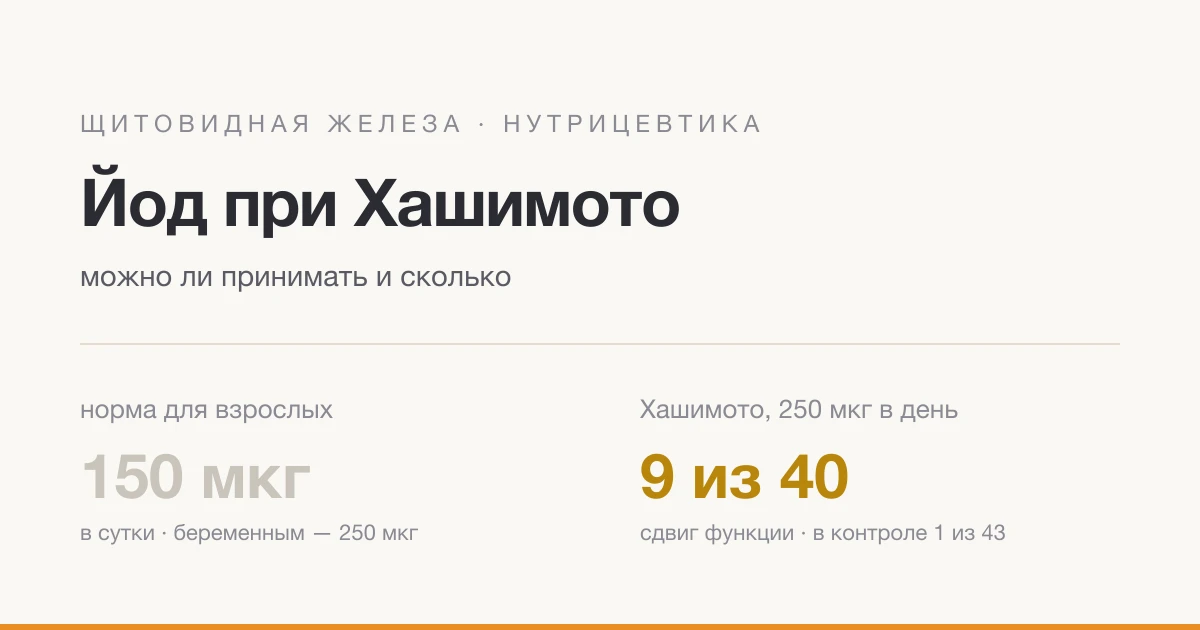
| Hashimoto’s, 250 µg of iodine a day for about 4 months, 1998 | 40 patients and 43 controls | Function shifted in 9 versus 1; in some it returned to normal after stopping |
| Iodine in edible seaweed, 2004 | 12 species | From 16 to 8165 µg per gram (one sample of kelp granules) |
| Seaweed products, UK, 2015 | 224 products | Iodine stated on 10%; 26 products, calculated per serving, could give more than 600 µg a day |
| Norm in pregnancy, WHO (per a 2009 review) | Pregnant women | 250 µg a day instead of 200 |
Not everything is clear: whether the rise in antibodies and subclinical hypothyroidism after salt iodisation is temporary is not yet known (Zimmermann MB Lancet Diabetes Endocrinol 2015. PMID 25591468[2]), and the authors of the Danish study write that the long-term consequences are yet to be studied (Pedersen IB Clin Endocrinol 2011. PMID 21521277[9]). Both papers are observations: a link, not a cause.
Who should be more careful
- With Hashimoto’s or raised TPO antibodies, do not start iodine supplements on top of food on your own: discuss the dose with your doctor and plan TSH monitoring.
- Older people with nodules that work on their own (functional autonomy): excess iodine can trigger acute overactivity (Burgerstein, Handbuch Nährstoffe 2015, p. 130).
- Before tests with iodine-containing contrast and when amiodarone is prescribed, tell your doctor about Hashimoto’s: these are common sources of large amounts of iodine (Sohn SY Endocr Rev 2024. PMID 38870258[8]).
Bottom line
The thyroid needs iodine in Hashimoto’s too: the main source is food and iodised salt, and the need rises in pregnancy. The caution concerns supplements on top of food and seaweed. A general overview of the topic is in the article Iodine and the thyroid. You can work out a plan and a testing schedule at a consultation.
This material is for information only and does not replace a doctor’s consultation. The iodine dose in Hashimoto’s and in pregnancy is chosen by a doctor based on test results.
References
- Leung AM Nat Rev Endocrinol 2014. PMID 24342882
- Zimmermann MB Lancet Diabetes Endocrinol 2015. PMID 25591468
- Zimmermann MB Am J Clin Nutr 2009. PMID 19088150
- Teng W N Engl J Med 2006. PMID 16807415
- Becker DV Thyroid 2006. PMID 17042677
- Korevaar TIM Thyroid 2026. PMID 42219800
- Teas J Thyroid 2004. PMID 15588380
- Sohn SY Endocr Rev 2024. PMID 38870258
- Pedersen IB Clin Endocrinol 2011. PMID 21521277
- Reinhardt W Eur J Endocrinol 1998. PMID 9703374
- Bouga M Foods 2015. PMID 28231201
Key facts
- The iodine norm for adults outside pregnancy and breastfeeding is 150 µg a day; higher intake is usually well tolerated, but in thyroid disease the risk of disruptions may be higher (Leung AM, Nat Rev Endocrinol 2014).
- WHO raised the iodine norm for pregnant women from 200 to 250 µg a day (Zimmermann MB, Am J Clin Nutr 2009).
- Among 3018 residents of three regions of China (an observation: a link, not a cause), over 5 years subclinical hypothyroidism appeared in 0.2% with mild iodine deficiency, in 2.6% with intake above the norm and in 2.9% with excess intake (Teng W, N Engl J Med 2006).
- In 40 people with Hashimoto’s and normal function, in an area with mild iodine deficiency, a supplement of 250 µg of iodine a day for about 4 months shifted thyroid function in 9; in the control group of 43, in 1 (Reinhardt W, Eur J Endocrinol 1998).
- Iodine in edible seaweed ranges from 16 µg per gram in nori to 8165 µg per gram in one sample of kelp salt-substitute granules (Teas J, Thyroid 2004).