Hypothyroidism
Hypothyroidism is a state where the thyroid gland produces insufficient T3 and T4. Prevalence in women over 40 reaches 10%. Diagnosis: TSH above 4.0 mIU/L + symptoms (fatigue, weight gain, hair loss, cold intolerance).
hub
Evidence-based protocols for hypothyroidism, AIT, insulin resistance, and endocrine dysfunctions
The thyroid gland is the master metabolic regulator. This hub aggregates articles on clinical protocols for hypothyroidism, autoimmune thyroiditis, insulin resistance, adrenal dysfunction, and other endocrine disorders. Each article cites peer-reviewed sources (Lancet, NEJM, JAMA, Endocrine Reviews) with direct PubMed links.
Last reviewed: 2026-06-01 · Dr. V. Pereligyn
Hypothyroidism is a state where the thyroid gland produces insufficient T3 and T4. Prevalence in women over 40 reaches 10%. Diagnosis: TSH above 4.0 mIU/L + symptoms (fatigue, weight gain, hair loss, cold intolerance).
AIT is autoimmune destruction of thyrocytes with positive anti-TPO and/or anti-TG antibodies. The most common cause of hypothyroidism in iodine-sufficient regions. Often triggered by EBV reactivation, selenium deficiency, HPA-axis stress, post-partum.
Hyperthyroidism is excess thyroid hormone production. Graves is the autoimmune variant with TSH-receptor antibodies (TRAB). Symptoms: tachycardia, weight loss, tremor, exophthalmos. Differentiated from subacute thyroiditis and toxic adenoma.
Thyroid nodules are detected in up to 50% of people on screening ultrasound. Most are benign. Red flags: nodule growth, calcifications, hypoechogenicity, irregular borders — require TIRADS stratification and fine-needle aspiration if indicated.
Isolated TSH elevation (4.0-10.0 mIU/L) with normal fT3 and fT4. Most cases do not require therapy, but with positive anti-TPO, symptoms, pregnancy or preconception — NDT or L-T4 initiation is warranted.
| Marker | Reference | What it means |
|---|---|---|
| TSH (thyroid-stimulating hormone) | 0.4-4.0 mIU/L | Optimum 1.0-2.5. Primary screening marker. Elevated in hypo-, suppressed in hyperthyroidism. |
| Free T4 (fT4) | 11.5-22.7 pmol/L | Prohormone, peripherally converted to T3. Decreased in overt hypothyroidism. |
| Free T3 (fT3) | 3.5-6.5 pmol/L | Active hormone. fT3/fT4 ratio reflects peripheral conversion quality. |
| Anti-TPO (thyroid peroxidase antibodies) | <5.6 IU/mL | AIT marker. Positive → high risk of overt hypothyroidism within 5 years. |
| Anti-TG (thyroglobulin antibodies) | <4.1 IU/mL | Adjunct AIT marker + post-thyroidectomy monitoring in oncology. |
| TRAB (TSH-receptor antibodies) | <1.75 IU/L | Specific for Graves disease. Level correlates with severity. |
| Reverse T3 (rT3) | individual | Elevated in stress, infection, low-calorie diets. High rT3 blocks peripheral T3 action. |
NDT contains T3 and T4 in a ~1:4 ratio, close to physiological. In some patients with L-T4 intolerance (persistent fatigue, brain fog despite "normal" TSH), switching to NDT improves symptoms and peripheral hormone activity. Targets: TSH 0.5-2.0, fT3 in the upper third of the reference range. Recheck every 6-8 weeks during titration. [1][2][3]
LDN 1.5-4.5 mg at bedtime — off-label option for confirmed EBV reactivation or concurrent CFS/post-viral fatigue. Mechanism via TLR4 + TRPM3 restoration on NK cells. No direct AIT RCTs; justified in patients with systemic autoimmune-overlap patterns. [1][2][3]
Selenium 200 mcg/day as selenomethionine reduces anti-TPO by 20-40% over 3-6 months (RCT data). Effect persists only while supplementation continues. Simultaneous iodine is controversial — worsens AIT in a subset of patients. [1][2][3]
Ferritin <50 ng/mL and vitamin D <30 ng/mL impair T4→T3 conversion and normal immune response. Maintaining ferritin 70-100 and vitamin D 50-80 ng/mL is a mandatory part of the AIT protocol. [1][2][3]
A 38-year-old woman presented with fatigue, hair shedding, and 6 kg weight gain over one year. Baseline: TSH 4.8 mIU/L, free T4 11.2 pmol/L, free T3 3.9 pmol/L, anti-TPO 480 IU/mL, anti-Tg 92 IU/mL, ferritin 28 ng/mL. Diagnosis: autoimmune thyroiditis with subclinical hypothyroidism. Intervention: NDT 32.5 mg/day titrated to 65 mg/day over 6 weeks, selenomethionine 200 mcg/day, iron bisglycinate 50 mg/day. At 6-month review: TSH 1.4 mIU/L, free T3 5.1 pmol/L, anti-TPO 180 IU/mL (−63%), weight −4.2 kg, ferritin 78 ng/mL. Symptomatic recovery achieved.
A 45-year-old man, routine screening. Baseline: TSH 6.9 mIU/L (repeat at 8 weeks 7.2), free T4 13.4 pmol/L, anti-TPO 95 IU/mL, serum selenium 68 mcg/L, vitamin D 22 ng/mL. Diagnosis: subclinical hypothyroidism with autoimmune features. Levothyroxine deferred given TSH <10. Intervention: selenomethionine 200 mcg/day, low-dose naltrexone 3 mg nightly, cholecalciferol 4000 IU/day. At 4-month review: TSH 2.6 mIU/L, anti-TPO 41 IU/mL (−57%), selenium 118 mcg/L, vitamin D 48 ng/mL. Euthyroid status reached without thyroid hormone replacement.
Lab reference for TSH is 0.4-4.0 mIU/L, but symptomatic optimum is 1.0-2.5. In AIT patients the target is 0.5-2.0. TSH above 2.5 with symptoms (fatigue, weight gain, hair loss) warrants evaluation of anti-TPO, fT3, fT4, and discussion of therapy initiation.
Levothyroxine contains only T4 (relying on effective peripheral conversion to T3). NDT (Thyroid-S, Armour) is natural porcine thyroid extract with T3 and T4 in ~1:4 ratio. With impaired conversion or persistent symptoms despite "normal" TSH, NDT is often better tolerated.
Iodine in AIT is controversial. In some patients, high-dose iodine intensifies the autoimmune process and raises anti-TPO. With AIT, iodine is reasonable only with proven deficiency (urinary iodine <100 mcg/L) and at physiologic doses 100-150 mcg/day.
Full AIT regression without relapse is rare. A realistic goal is 50-80% anti-TPO reduction, normalized TSH, and symptom resolution. This is achieved by combining adequate replacement (NDT/L-T4), selenium, ferritin and vitamin D maintenance, and trigger elimination (stress, EBV, sleep deficit).
First TSH + fT3 + fT4 recheck — 6-8 weeks after initiation or dose adjustment. Earlier — hormones have not reached a new steady-state. After stabilization — every 3-6 months. In pregnancy — every 4 weeks in the first trimester.
Directly — no. But chronic stress via the HPA-axis raises rT3, impairs T4→T3 conversion, and activates autoimmune processes. In genetically susceptible patients, prolonged stress is often the trigger for AIT manifestation.

TSH is the conductor of the thyroid, but eight more signals prompt it. A table of the signals, how to take the test honestly and what the studies showed.

A small gland with a big job: seven facts about the thyroid from textbooks, reviews and guidelines. How the hormone store works, why it needs iodine and when to test TSH.

A five-day menu of ordinary foods without grains or bread: three dishes a day, the plate rule, protein at the start of a meal, 25-29 g of fibre and a short walk after eating. What human studies showed.

Dill capsules for 90 days in 68 people with benign thyroid nodules: nodules on ultrasound were smaller than in the placebo group. One small study: dill supplements follow-up with a doctor but does not replace it.

Five thyroid remedies with human study data: curcumin, probiotics, vitamin D, myo-inositol with selenium and natural desiccated thyroid. What each one offers and how they are combined into one plan.

Three things that blur the thyroid picture after 50: biotin “for hair” before a test, excess iodine from seaweed, and a TSH range read without adjusting for age. What studies in people showed and what to do.
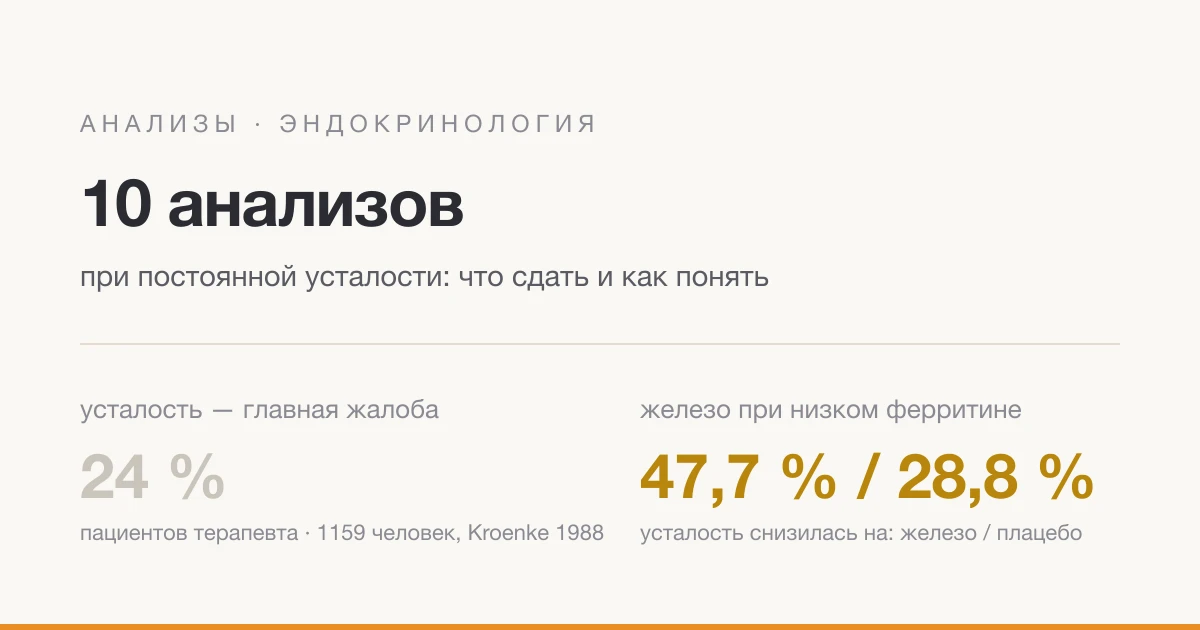
A guide: ten blood tests for constant fatigue — ferritin, thyroid hormones, vitamins D and B12, glucose and glycated haemoglobin, morning cortisol, haemoglobin, a liver enzyme and an inflammation marker — with reference points from guidelines and studies in two unit systems.
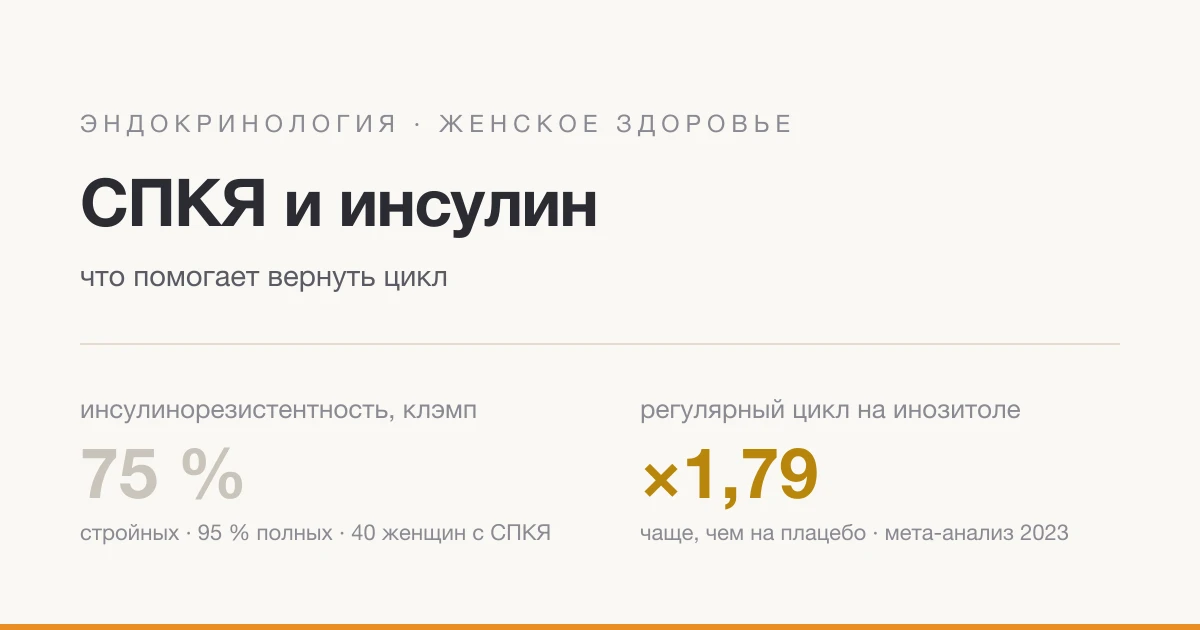
Polycystic ovary syndrome is not a disease of the ovaries but a metabolic disorder, and one of its key links is insulin. The good news: insulin can be influenced. Briefly and in plain words: how the diagnosis is made, the five pillars of a holistic approach, what studies of inositol, berberine and spearmint tea showed, and which tests to discuss with your doctor.
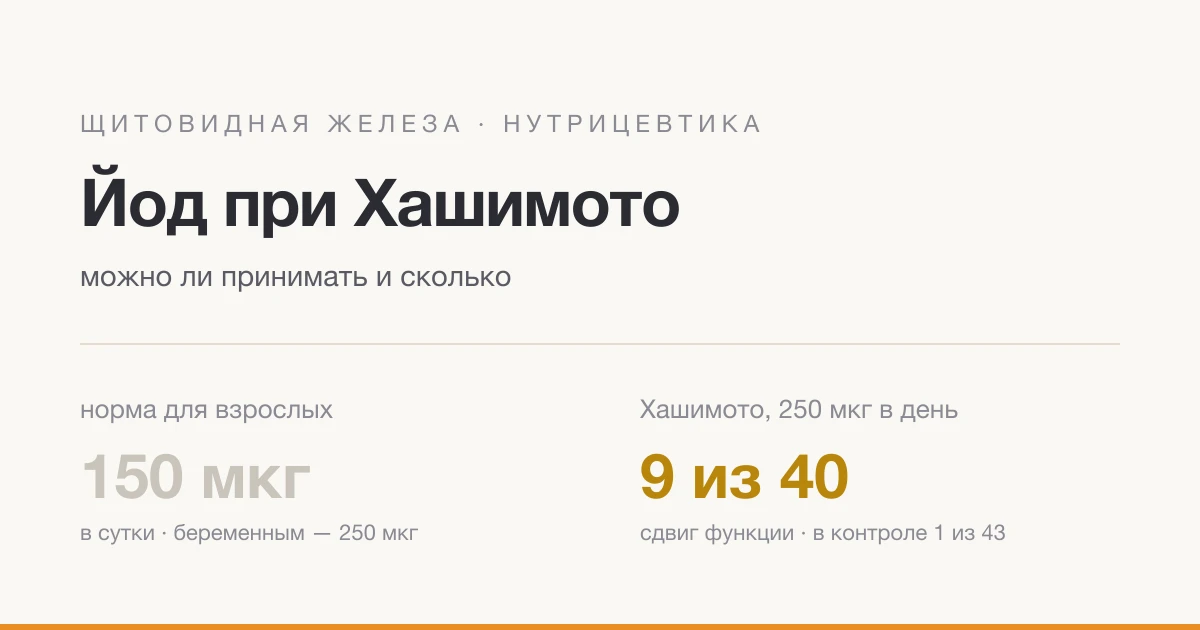
The thyroid needs iodine, including in Hashimoto’s, and more of it is needed in pregnancy; the main source is food and iodised salt. In plain words: how much iodine is needed, where it comes from, what a study in people with autoimmune thyroiditis showed and when to be careful with supplements and seaweed.
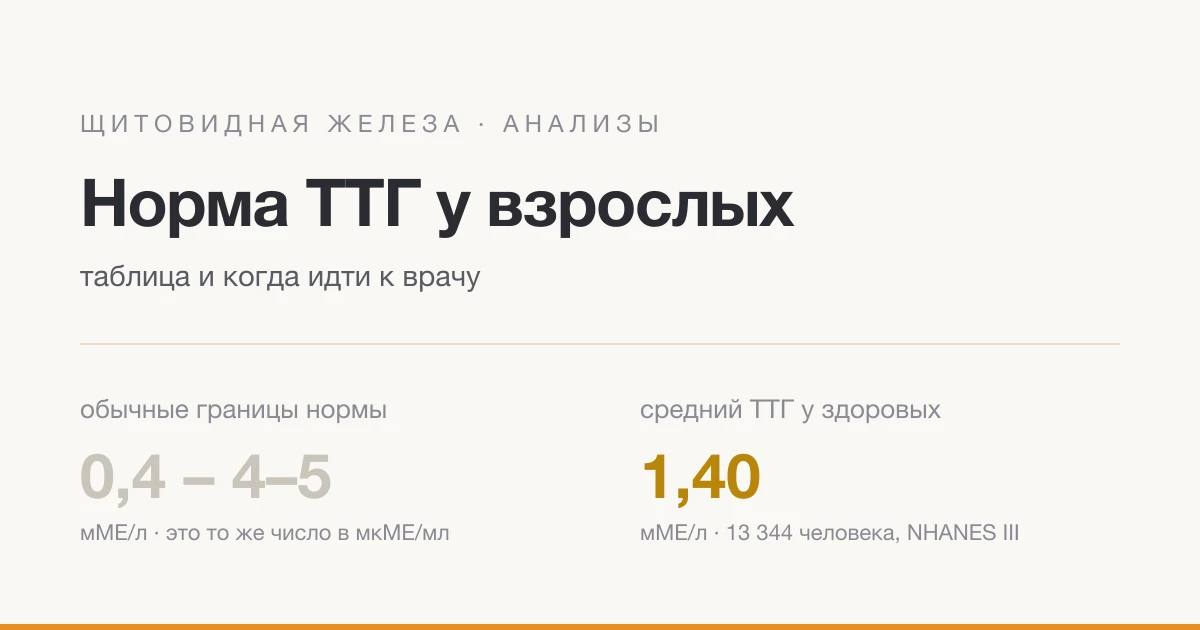
TSH is a simple, inexpensive test and the first step in checking the thyroid. The usual normal range is roughly 0.4 to 4–5 mIU/L (0.4 to 4–5 µIU/mL); it is higher with age, and a mild rise often goes away on its own; an abnormal result is confirmed by a repeat test. A simple table: what your result means, when to retest, when to see a doctor and what distorts the test.
Hands and feet that feel cold even in a warm room are a common complaint. The good news: many causes are easy to check — some are found with blood tests, some on examination, and many of them are treatable. Briefly and in plain words: six causes, which tests to discuss with your doctor, and which signs mean you should not put off a visit.
Fatigue and low energy occur both with a shortage of thyroid hormones and with burnout. The good news: a simple blood test checks how the thyroid is working, and serious diseases are rare among the causes of fatigue. Briefly and in plain words: what signs occur with hypothyroidism, what burnout is, and what else to check.

Thyroid testing starts with one test — TSH — and the rest are added as needed. In plain words: what TSH, free T4 and T3 show, which antibodies explain the cause of the problem, when an ultrasound is really needed and how to prepare so you don't get a false result.

One patch for 7 days instead of daily tablets: estradiol relieves hot flushes, levonorgestrel protects the uterus, and the transdermal route does not raise the risk of thrombosis. What this patch is, who needs the sequential version and who the continuous one, and under which names it is sold in France, Italy, Germany and the UK.
Hormone replacement therapy (HRT) is the most powerful remedy for hot flushes: 75 % fewer than on placebo. Which oestrogens and progestogens exist, why a patch is safer than a tablet, which regimen is needed when the womb is intact, what to do if hormones are contraindicated — in one overview with tables from NICE, BMS and The Menopause Society.

A guide to the Stress Axis questionnaire: how sleep loss raises evening cortisol and how evening light and caffeine interfere with sleep, what the four areas of the result mean, and which signs must not be written off as stress. It also explains how to read cortisol, ferritin, TSH, and B12 with the test method in mind.

One person can take a thyroid pill and iron if the two are separated in time — though even the gap does not help everyone. We look at where the 4 hours came from and why some leaflets say 2, what a small study of taking them together showed, why iron is not stopped when there is a deficiency, and when it is worth checking ferritin.
GLP-1 drugs are proteins, and the stomach digests them: nearly all are injections, and the semaglutide tablet must be taken fasting. Orforglipron is built differently and therefore works as a tablet taken with or without food. What the trial in 3127 people showed, why the pill is weaker than the injection and what it is for anyway, and what the label says in small print.

The autoimmune protocol in Hashimoto's thyroiditis has been tested in two studies, and in the first, people on a supported programme felt markedly better: quality of life rose and symptom burden fell. Here is what was measured, how to follow the phases of the protocol, which tests to do before starting, who should see a doctor first and which supplements in thyroiditis are backed by data.

A gluten-free diet in Hashimoto's thyroiditis has a clear address: people with celiac disease, with gluten-related conditions and with GI complaints. Here is what the only meta-analysis on the topic found, who the diet helps, what must be tested BEFORE gluten is removed, and how to build a gluten-free diet that stays nutritious.

By its structure vitamin D is closer to a hormone, and receptors for it sit in immune cells and in the thyroid gland itself. In autoimmune thyroiditis it lowers thyroid antibodies, and in a large trial people taking it developed new autoimmune diseases less often. Here is what the studies show, how to set the dose by a blood test, when an injection is justified and why smaller doses more often beat one big dose a year.
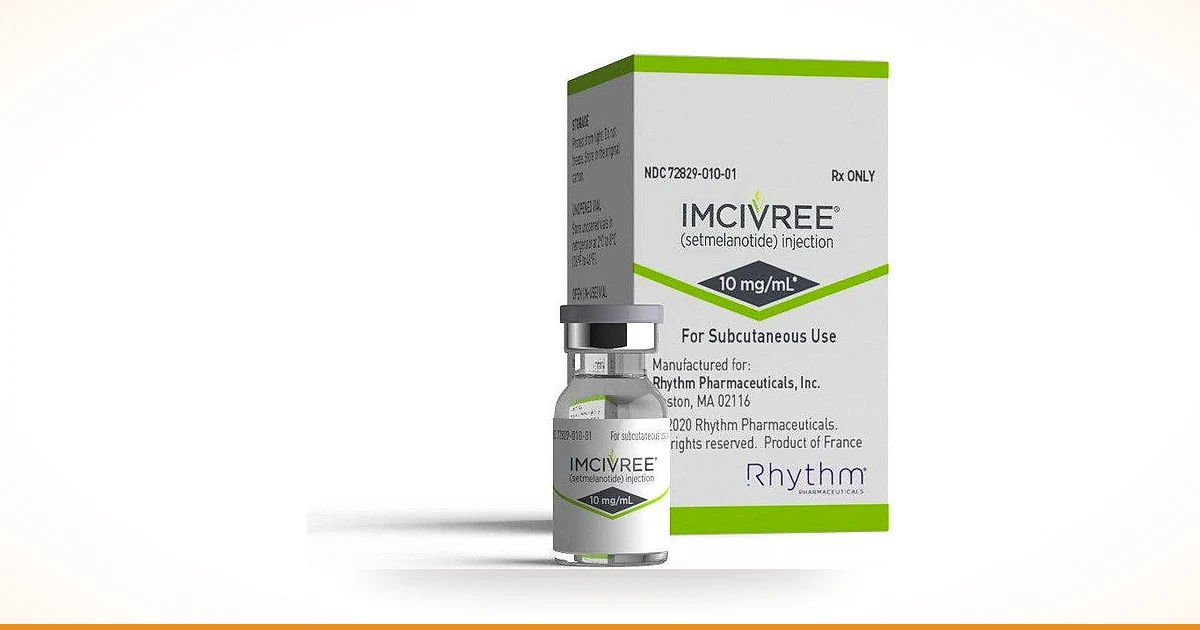
There is a form of obesity that has nothing to do with overeating or willpower: the mechanism that tells the brain it is full is broken. In POMC, PCSK1 or LEPR deficiency, in Bardet-Biedl syndrome and after damage to the hypothalamus, the melanocortin-4 pathway fails to carry the signal, and the hunger that follows cannot be negotiated with. Setmelanotide switches that pathway back on. A short guide: who it is for and, more importantly, who it is not for; the mechanism; dosing by age; what the trials showed; and what the effect costs.

Depression and anxiety are linked to the thyroid — and that link can be measured and factored into treatment. In euthyroid Hashimoto’s, with normal TSH and fT4, the lifetime odds of depression are 6.6× higher and of generalized anxiety disorder 4.9× higher (case-control study). Adding T3 to an antidepressant after two failed courses produced remission in 24.7% of patients (STAR*D). I review which mental illnesses are linked to thyroid disease, which tests to run, and who should see a doctor first.

TSH is a pituitary hormone: it reflects feedback, not thyroid function directly. The full panel — TSH, free T4 and T3, antibodies, ultrasound and cofactors — sees what a single number misses: early autoimmune thyroiditis, impaired T4 → T3 conversion, central hypothyroidism. I cover the narrow 2.5 range, antibodies, selenium, iodine, TI-RADS and the decision principle.

T3 is the only thyroid hormone that actually works. And it works not in blood but inside the cell, at the nuclear receptor. Blood is only a transport phase. Some women with normal TSH have cellular hypothyroidism and suffer with full symptoms despite "normal" labs. Here is the biology of T3, T4→T3 conversion, the hidden forms of deficiency, and the full laboratory panel.

TSH normal, free T4 normal, and the patient is falling apart with fatigue, cold intolerance, weight gain, and broken sleep. The classic "your labs are fine" trap. In reality, chronic stress shuts the thyroid down at three different levels, and you only see it on a properly built panel: fT3, rT3, morning cortisol, ferritin, selenium. Here is the mechanism, the exact numbers, and an 8-week recovery protocol.

Two to six weeks after an acute viral infection, the patient returns with "I am not myself" complaints: palpitations, sweating, anxiety — or the opposite, fatigue, edema, apathy. The post-viral thyroid can follow one of three clinically distinct paths. Treatment for each is different. Blanket therapy makes things worse. This review covers how to tell the scenarios apart, what to measure, and when not to prescribe levothyroxine.

Anti-TPO antibodies are the key to diagnosing autoimmune thyroiditis. Here is when the test changes management, how to read the titer (35 / 100 / 1000 IU/mL), what to order alongside it, where selenium actually reduces antibody levels by 30–40%, and what matters in pregnancy and IVF.

Hashimoto's thyroiditis is not a snapshot diagnosis — it is a slow autoimmune process that unfolds over 10–30 years through four sequential stages. Understanding the stage changes clinical strategy: starting levothyroxine in stage 1 is blind therapy; withholding it in stage 3 is malpractice. This article maps the four stages with markers, timing, and the protocol grounded in ATA Guideline.
Up to 50% of adults have thyroid nodules on ultrasound, and the vast majority are benign. The decision to biopsy follows clear rules — the TIRADS category combined with size, not the mere fact of detection. This review covers the practical ACR TIRADS scale, size thresholds for biopsy, the surveillance protocol, and where Bethesda fits after FNA.

Selenium is the obligate cofactor of deiodinases and glutathione peroxidases, and the thyroid gland concentrates it more densely than any other organ per gram of tissue. In Hashimoto's thyroiditis, 200 mcg for 6 months reduces TPO antibodies by 30–40%; in mild Graves' orbitopathy, selenium slows progression. This is the analysis: why exactly this dose, which form works, who selenium is indicated for, and how to monitor therapy.

Pregnancy needs its own TSH norms: until weeks 18–20 the fetal CNS develops entirely on maternal thyroid hormones, and trimester-specific TSH targets help support mother and child in time. Here are trimester-specific TSH targets, tactics for anti-TPO positive women, levothyroxine dosing, and iodine prophylaxis per ATA 2017 (PMID 28056690).

Vitamin D raises calcium absorption but does not decide where that calcium goes. Vitamin K2 (menaquinone MK-7) does: into bone via osteocalcin activation, or into arterial walls when deficient. In Hashimoto autoimmune thyroiditis this pair is critical — hypothyroidism itself increases the risk of osteoporosis and vascular calcification. Exact doses, 25(OH)D targets, monitoring, contraindications, and the protocol with levothyroxine.

After thyroid removal, 10–15% of patients on adequate L-thyroxine and "normal" TSH continue to report fatigue, weight gain, cognitive issues. This is not "all in your head" — it is incomplete T4-to-T3 conversion. I break down the US protocol for NDT: composition, brands (Armour, NP Thyroid, Niva), starting doses, titration, and when L-thyroxine remains the correct choice.

Naltrexone at 1.5–4.5 mg/day (10 times lower than addiction-medicine dosing) ceases to act primarily as an antagonist and becomes an immunomodulator. Short nocturnal blockade of μ-opioid receptors produces a rebound increase in endogenous endorphins, TLR4 blockade on microglia, and a Th17 / Treg shift toward tolerance. In Hashimoto thyroiditis, LDN is a third-line candidate when TPO antibodies remain elevated despite an adequate L-T4 dose and corrected selenium and vitamin D deficiencies. I review the mechanism, titration protocol, expected time to effect, and settings where LDN should not be used.
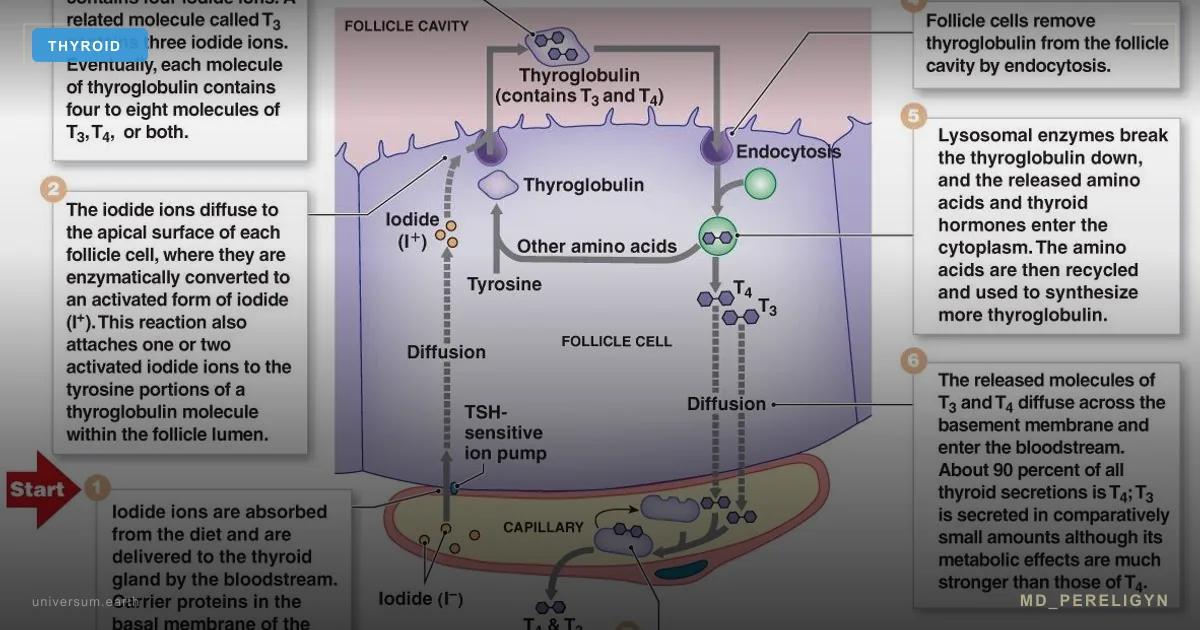
Thyroxine (T4) is a prohormone; the active hormonal form is triiodothyronine (T3). The D1/D2 deiodinase enzyme in the liver, kidneys, intestine, and brain is responsible for T4 → T3 conversion. Deiodinase is a selenoprotein; iron and zinc support thyroid hormone metabolism (deiodinase data mostly from animals). If the enzyme works poorly, the tablet remains in the bloodstream while tissues remain without a signal. By the European Thyroid Association estimate, 5–10% of patients on an L-thyroxine dose that is adequate by TSH keep symptoms: fatigue, dry skin, hair loss, weight gain, brain fog. This is functional hypothyroidism: a state in which TSH is normal, fT4 is normal, but tissue T3 is not. I review four mechanisms of impaired conversion, markers, target ranges, and a holistic restoration protocol.

When labs show elevated prolactin, pregnancy, medications, hypothyroidism and renal failure are excluded first. If no cause is found, the main pathological cause is a prolactinoma, and pituitary MRI is needed. Almost all causes act through one link — dopaminergic control — and understanding it helps both diagnosis and treatment.

L-thyroxine + OCPs to a young woman "just in case" — this is not treatment, it is intervention into the endocrine axis without diagnosis. Let us examine how ethinyl estradiol distorts thyroid labs and why the standard "elevated TSH → give thyroxine" approach often contradicts current clinical guidelines.

Iodine is essential raw material for thyroid hormones, but 80% of cases of its inefficacy or harm are not about dose — they are about systemic context. When selenium and iron are missing, iodine does not heal — it fuels inflammation. Here is the five-stage model: from cellular uptake to T4→T3 conversion.
When you aggressively cut calories, fast, and live in stress, the body does not turn on fat burning — it turns on survival mode. First water leaves and it seems to work. Then reverse T3 rises, active T3 falls, mitochondria slow, you feel cold, swollen, foggy. And weight stalls or creeps up. Here is how to escape this trap.

The term "adrenal fatigue" dominates integrative medicine discussions, yet it has never been recognized as a legitimate medical diagnosis. The real issue — HPA axis dysregulation — is well-documented in peer-reviewed literature and has measurable biomarkers and evidence-based treatment protocols — and a cortisol curve is not one of its diagnostic tools.

After age 40, testosterone declines by 1-2% annually. But age-related decline is not always benign. We examine when TRT is genuinely warranted, which labs are essential, and how to optimize testosterone naturally before committing to lifelong therapy.
Menopause affects every woman. But hot flashes, insomnia, anxiety, and bone loss are not inevitable. We examine the difference between bioidentical and synthetic hormone therapy, reinterpret the WHI study, and outline a personalized approach to menopausal hormone therapy.
Insulin resistance is one of the key mechanisms of PCOS, and it occurs even at normal weight. Birth control pills are first-line for irregular cycles and hyperandrogenism, but they do not remove metabolic risk, which has to be assessed separately. We examine the pathophysiology, diagnosis, and treatment according to the 2023 international guideline.

Pregnenolone — the precursor to every steroid hormone in the body — occupies a unique position at the intersection of endocrinology and neuroscience. During chronic stress and burnout, its levels decline among the first, triggering a cascade of hormonal disruption.

Labs are normal but symptoms persist? Symptoms persist in 5–10% of levothyroxine-treated patients with normal TSH: fatigue, weight gain, brain fog. The problem isn't the patient — it's the approach.
Dr. Pereligyn offers in-person and online consultations.
Book a consultation