in pictures and a few words
What it is and why it matters
Menopause is when periods have been absent for 12 months in a row, on average around age 51. Hormone therapy can make this time easier.
- The ovaries release fewer and fewer female hormones; swings may begin 5–10 years before this
- Most often — hot flashes, night sweats and poor sleep; anxiety and low mood also occur
- Hot flashes often last for years
Why hormones were feared
One large study found more breast cancer, strokes and blood clots in women on hormones. Its data were later re-examined.
- The women were on average over 60, more than 10 years past menopause
- They were given synthetic hormones, not ones identical to their own
- In women aged 50–59 taking estrogen alone, death and heart attack outcomes were better than in older women
Your own vs foreign hormones
Bioidentical hormones are molecules exactly like a woman’s own hormones. Synthetic ones are different molecules.
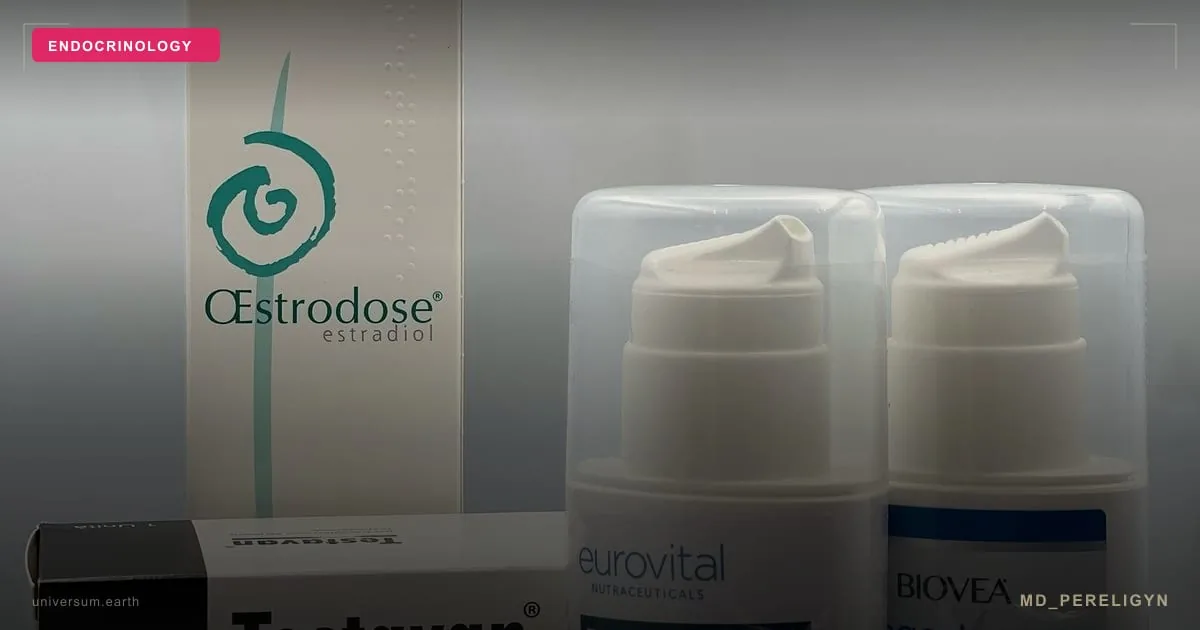
- Estradiol — a patch, a gel or a pellet under the skin every 3–5 months
- Progesterone — capsules by mouth or vaginally; estriol — locally for dryness
- Synthetics — estrogens from pregnant mares’ urine and man-made progesterone look-alikes
Through the skin is gentler
Estradiol in a patch or gel is absorbed through the skin and does not pass through the liver first.
- Does not boost blood clotting and does not affect triglycerides — one of the blood fats
- The risk of clots does not rise — unlike estradiol tablets
Progesterone at bedtime
Progesterone identical to your own is taken before sleep. It calms and eases anxiety.
- The usual dose is 100–200 mg at bedtime
- Protects the inner lining of the uterus from overgrowth while estrogen is taken
Bones and heart
Estrogen helps protect the bones and, if started early after menopause, the heart too.
- Bones lose strength fastest in the first 5–7 years after menopause
- On hormone therapy there were almost a quarter fewer fractures, and the hip bone became denser
Dryness and frequent cystitis
Dryness, pain during sex, burning and frequent cystitis after menopause do not go away on their own. Local products with estrogen help.
- A cream, vaginal tablets or a ring; treatment is usually long-term
- At low doses, hormone levels in the blood are no higher than usual after menopause
- No need to add progesterone to them
Important. After breast cancer, safety data on local estrogen products are still scarce — they are prescribed only together with the oncologist.
Check-up before starting
Before starting, you have blood tests and your breasts and uterus are checked. This is how the doctor decides whether therapy suits you and in what form.
- Blood tests: hormones, thyroid, sugar, blood fats
- A mammogram within the last year and a pelvic ultrasound
- Then check-ups at 6–12 weeks, at six months and at one year
Who should see a doctor first
Hormones are prescribed only by a doctor. They are not given during pregnancy, with current or past breast cancer, or with tumors that grow on hormones.
- Clots in the veins or lungs, a heart attack or stroke in the last six months
- Vaginal bleeding without a clear cause, liver disease that impairs its function
- Migraine with aura, gallstones, a tendency to clots, very high blood pressure — the doctor decides
Important. Starting hormones for the first time after 60 or more than 10 years after menopause is not recommended. Those already taking them may continue under supervision.
In one sentence
Hormones identical to your own — estradiol through the skin and progesterone — ease hot flashes and protect the bones. They are started early after menopause, after a check-up and with a doctor.
Introduction: Menopause Is Not a Disease — But It Is Not "Just Aging" Either
Menopause is defined retrospectively after 12 months of amenorrhea. Average onset: age 51. Perimenopause can begin 5-10 years earlier, characterized by fluctuating estrogen and progesterone levels.
The SWAN Study (Study of Women's Health Across the Nation) found that 80% of women experience vasomotor symptoms (hot flashes, night sweats), 60% have sleep disturbances, 40% report cognitive changes, and 30% develop anxiety or depression. Mean duration of vasomotor symptoms: 7.4 years. In 10% of women, symptoms persist beyond 12 years.
The Physiology of Menopause
Depletion of the ovarian follicular reserve leads to progressive decline in estradiol (the primary reproductive estrogen), progesterone, and inhibin B. FSH and LH rise compensatorily. Estradiol drops from 100-400 pg/mL to 10-20 pg/mL, affecting over 400 bodily functions: thermoregulation, bone metabolism, lipid metabolism, and neurotransmission.
The WHI Study: Groundbreaking — and Widely Misinterpreted
The Women's Health Initiative (WHI, 2002) remains the most cited study in menopausal hormone therapy. Key findings: conjugated equine estrogens (CEE, Premarin) plus medroxyprogesterone acetate (MPA, Provera) increased breast cancer risk by 26%, stroke by 41%, and thromboembolism by 113%.
However, later publications — a WHI reanalysis (Manson et al., JAMA, 2013) and the separate ELITE RCT (Hodis et al., NEJM, 2016) — revealed critical nuances:
- Average participant age was 63 (10+ years post-menopause)
- Synthetic animal-derived hormones were used, not bioidentical compounds
- In women aged 50–59 on estrogen without MPA, mortality and myocardial infarction outcomes were more favorable than in older women (Manson et al., JAMA, 2013)
- In the ELITE RCT (643 women), estradiol started within the first 6 years of menopause slowed carotid wall thickening (Hodis et al., NEJM, 2016)
- Estrogen-only therapy (without MPA) in hysterectomized women reduced breast cancer risk by 23%
Bioidentical vs Synthetic Hormones: Key Differences
| Class | Bioidentical | Synthetic |
|---|---|---|
| Estrogen | 17β-estradiol | CEE (Premarin) |
| Progestogen | micronized progesterone | MPA (Provera) |
| Breast cancer (E3N) | RR 1.00 | RR 1.69 |
| VTE transdermal | no increase | oral raises |
Bioidentical hormones are molecules chemically identical to endogenous human hormones:
- 17beta-estradiol — identical to ovarian estradiol. Available as transdermal patches, gels, and pellets
- Micronized progesterone (Prometrium/Utrogestan) — identical to endogenous progesterone. Available as oral or vaginal capsules
- Estriol — a weak estrogen used topically for urogenital atrophy
Clinical Evidence for Bioidentical Hormones
The KEEPS trial (Kronos Early Estrogen Prevention Study, 2012): transdermal estradiol in women aged 42-58 showed no increase in atherosclerosis markers while significantly improving vasomotor symptoms.
The E3N French cohort study (Fournier et al., Breast Cancer Research and Treatment, 2008): transdermal estradiol combined with micronized progesterone showed NO increased breast cancer risk (RR 1.00), while synthetic progestins raised risk (RR 1.69).
A meta-analysis in Climacteric (2019): transdermal estradiol, unlike oral estrogen, does not increase venous thromboembolism risk.
Bioidentical Therapy Formulations
Transdermal Patches and Gels
Estradiol patches (0.025-0.1 mg/day) or gels bypass hepatic first-pass metabolism, avoiding increases in clotting factors and triglycerides.
Subcutaneous Estradiol Pellets
Implanted every 3-5 months for stable estradiol levels without daily procedures. Particularly effective for severe vasomotor symptoms unresponsive to other delivery methods.
Micronized Progesterone
100-200 mg at bedtime. Provides anxiolytic and sedative effects through its metabolite allopregnanolone (a GABA receptor agonist). Protects the endometrium from hyperplasia during estrogen therapy.
Custom Compounded Formulations
Compounding pharmacies prepare personalized formulas (creams, gels, capsules) with precise hormone ratios. Advantage: individualized dosing. Limitation: lack of standardized quality control.
Bone and Cardiovascular Protection
Bone loss accelerates during the first 5-7 years post-menopause — up to 3-5% annually. Estrogen therapy slows bone loss and lowers fracture risk: in the WHI RCT (Cauley et al., JAMA, 2003; 16,608 women aged 50–79, CEE + MPA) fractures were 24% fewer and total hip BMD rose 3.7% over 3 years [PMID: 14519707[1]]; the choice between it and non-hormonal agents is made with the doctor [PMID: 28093732[2]].
Cardioprotection: the DOPS trial (Danish Osteoporosis Prevention Study, Schierbeck et al., BMJ, 2012) — 10 years of MHT initiated in early menopause reduced heart failure and myocardial infarction risk by 52% with no increase in cancer risk.
Frequently Asked Questions
Is hormone therapy safe after age 60? Initiating MHT more than 10 years after menopause or after age 60 is not recommended due to elevated cardiovascular risk. However, women already on MHT may continue under supervision.
Do bioidentical hormones increase cancer risk? Transdermal estradiol plus micronized progesterone is the safest combination. The French E3N cohort found no increased breast cancer risk.
How long can MHT be taken? Current guidelines (IMS, 2023): the decision is individualized with no arbitrary duration limit. Annual reassessment of risk-benefit ratio is recommended.
How do compounded hormones differ from pharmaceutical-grade? The molecules are identical. The difference lies in delivery form and dosing precision. FDA-approved products undergo standardized quality control; compounded formulations do not.
Is progesterone needed after hysterectomy? For endometrial protection, no: after hysterectomy estrogen is given without a progestogen. Bedtime progesterone is sometimes added for sleep — an individual decision by the doctor.
This article is for educational purposes only and does not constitute medical advice. Always consult a qualified healthcare professional before starting any treatment.
🌀
Laboratory Monitoring Protocol on Bioidentical Hormone Therapy
The article cites transdermal estradiol dosing in micrograms but provides no laboratory targets to confirm physiological replacement. Without monitoring, "bioidentical" remains a marketing label rather than a measurable clinical state. The following biochemical framework is consistent with North American Menopause Society and Endocrine Society positions.
Salivary and capillary "hormone panels" marketed by compounding pharmacies show poor correlation with serum levels and high intra-assay variability; they should not guide dosing. When a patient arrives with prior salivary results, repeat serum testing before any titration decision.
🌀
Absolute and Relative Contraindications
The article advocates therapy initiation in early postmenopause but does not define who should not be treated. Patient selection determines the benefit-risk ratio more than formulation choice.
Relative contraindications requiring individualized risk discussion. Migraine with aura — transdermal route only, because oral estrogen increases ischemic stroke risk in this population. Uncontrolled hypertension above 160/100 mmHg should be normalized before initiation. Symptomatic gallbladder disease — oral estrogen increases cholelithiasis risk; transdermal is preferred. Hypertriglyceridemia above 4.5 mmol/L (400 mg/dL) — oral estrogen raises triglycerides 24–38% via first-pass hepatic effect and can precipitate pancreatitis; transdermal lowers or does not change triglycerides. Family history of breast cancer is not a contraindication; BRCA1/2 carriers without prior cancer may receive short-term therapy after risk-reduction surgery with shared decision-making. [PMID: 30447915[3]]
Conditions requiring specialist clearance before initiation. Endometriosis history may flare on estrogen monotherapy and mandates continuous combined regimen. Uterine fibroids larger than 5 cm may grow; baseline pelvic ultrasound establishes a reference for surveillance. Otosclerosis can progress on systemic estrogen and warrants ENT consultation. Systemic lupus erythematosus without antiphospholipid antibodies is not a contraindication; with antiphospholipid antibodies, therapy is contraindicated. Patients on aromatase inhibitors for breast cancer prevention should not receive systemic estrogen.
🌀
Genitourinary Syndrome of Menopause: Local Estriol Protocol
Genitourinary syndrome of menopause (GSM) affects approximately 50% of postmenopausal women and includes vaginal dryness, dyspareunia, urinary urgency, and recurrent urinary tract infection. Systemic therapy resolves GSM in only 40–75% of cases; the remainder require local treatment. The article mentions estriol once — concrete dosing follows.
🌀
Discontinuation and Reassessment
No menopausal therapy is intended to be permanent without periodic reassessment. The article omits exit strategy, which is as clinically important as initiation.
References
Key facts
- Average menopause onset is age 51; vasomotor symptoms last a mean of 7.4 years (SWAN).
- 80% of women have vasomotor symptoms, 60% sleep disturbance, 30% anxiety or depression.
- Estradiol drops from 100–400 to 10–20 pg/mL, affecting over 400 bodily functions.
- Transdermal estradiol + micronized progesterone: breast cancer RR 1.00 (E3N cohort).
- Bone loss reaches 3–5% per year in the first 5–7 years post-menopause.



