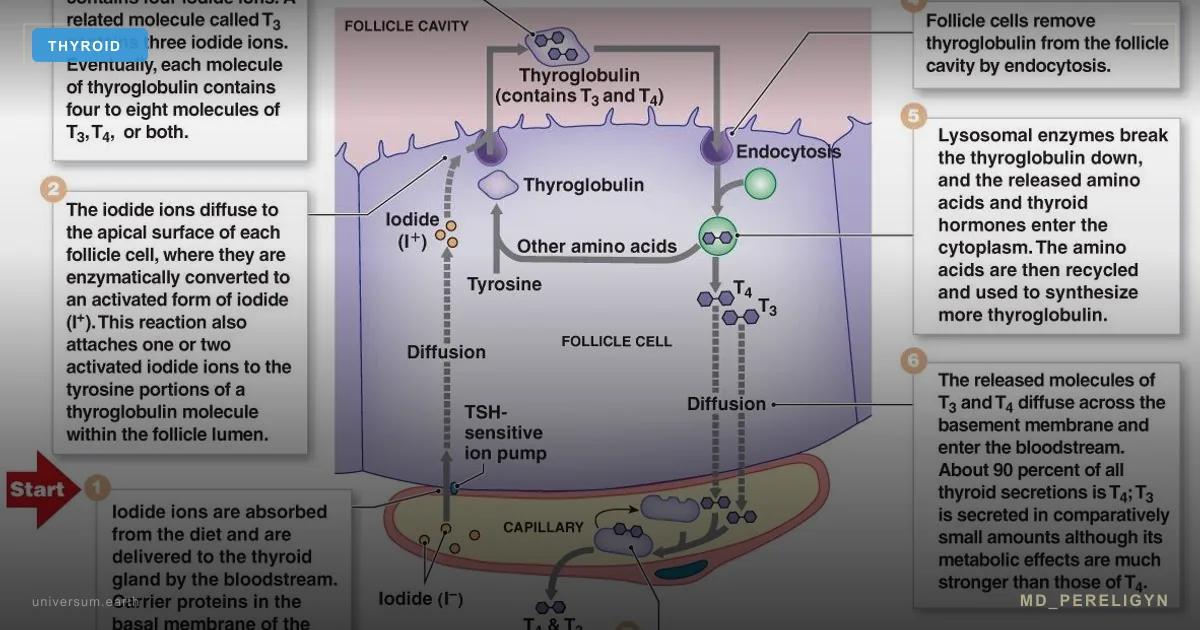
in pictures and a few words
What it is and why it matters
A thyroid pill is the storage form of the hormone. Cells run on another, working form, which the body makes from the storage form itself.
- The conversion happens mostly not in the thyroid but in the liver, kidneys, brain and muscles
- A helper enzyme does it: it contains selenium, and it also needs iron and zinc to work
Tests normal, but no energy
Some people on a pill dosed by their blood test still have fatigue, feeling cold, dry skin, hair loss and constipation.
- The main thyroid test and the storage hormone are normal, but there is little working hormone
- This is a reason to check the hormone conversion, not to blame “laziness”
- The problem shows up in a blood test if you take more than the main test
“Winter mode”
Under stress, inflammation and hunger the body saves energy: the storage hormone goes into an inactive form. With long-lasting stress this mode can get stuck for a long time.
- Constantly high cortisol, the stress hormone, gets in the way, including from lack of sleep
- Long-lasting inflammation gets in the way: belly fat, hidden infections, sore gums
- Often there are several causes at once, so selenium alone helps only partly
Selenium, iron, zinc
The helper enzyme contains selenium, and to work it also needs iron and zinc. Shortages are made up based on tests.
- Selenium is often short where soil is poor in it, including Ukraine and Poland
- Selenium: no more than 400 mcg a day, in pregnancy no more than 200; excess harms hair, nails and nerves
- Iron: based on an iron-stores test, and at least 4 hours apart from the thyroid pill
Which tests to take
Besides the main thyroid test, these help: the working and inactive hormone, thyroid antibodies, selenium, iron stores, zinc, vitamin D and an inflammation marker.
- Cortisol: in the morning, from blood, to rule out weak adrenal glands
- A daily saliva cortisol curve does not make a diagnosis; stress is assessed with questionnaires
- Hormone ratios are a doctor’s practice guide, not a strict cut-off
How to take the pill
The pill is absorbed worse near food, coffee and some supplements. If the test is off on an adequate dose, absorption is checked first.
- On an empty stomach with water; breakfast and coffee no sooner than an hour later
- Iron, calcium and some heartburn remedies: at least 4 hours apart from the pill
- High-dose biotin “for hair” distorts the test: stop it two days before
Sleep, light and food
Anything that lowers stress and inflammation helps.
- Sleep 7–9 hours, in bed before 11 pm
- 10 minutes of daylight within the first hour after waking
- Mediterranean-style food: fish, vegetables, beans, olive oil
No dose increase for energy
Raising the pill dose to get rid of fatigue is a common mistake. It does not add energy, and extra hormone is linked to heart rhythm problems and fragile bones.
- Only a doctor changes the dose, based on tests
- Only a doctor adds the second, working hormone, after several months of the plan
- Do not start it yourself: without monitoring it raises the risk to heart and bones
Important. Do not stop the pill yourself, even if you feel better on supplements: with a marked hormone shortage this is dangerous.
Who should see a doctor first
Fatigue is not only about the thyroid. First rule out B12 and folic acid shortage, anaemia, pauses in breathing during sleep, depression and diabetes.
- Suspected weak adrenal glands: morning blood cortisol first, then any dose change
- Pregnancy: see a doctor as soon as the test is positive; the hormone need grows
- Amiodarone, lithium, estrogen pills, propranolol: discuss with your doctor
Important. Palpitations, tremor or weight loss on the same dose: see an endocrinologist; do not change the dose yourself.
In one sentence
If the test is normal on the pill but you have no energy, check whether the hormone is converted into its working form and fix the cause. Only a doctor changes the hormone dose.
Introduction: symptoms despite a “normal” TSH
According to the 2012 European Thyroid Association (ETA) guideline, 5–10% of patients receiving L-thyroxine replacement therapy at a biochemically adequate dose (TSH in the reference range) continue to have residual symptoms of hypothyroidism: fatigue, dry skin, weight gain, hair loss, brain fog, cold intolerance, tendency toward constipation, and reduced libido (PMID 24782999).
In the community-based study by Saravanan and colleagues, among patients on L-thyroxine with a normal TSH, signs of psychological distress on the GHQ-12 questionnaire were found in 34.4% versus 25.6% of age- and sex-matched controls; the difference held after adjustment for chronic disease and medication (PMID 12390330).
The standard cardiologist-endocrinologist response is: “TSH is normal; go home, the problem is not the thyroid.” But the problem is precisely in the thyroid axis: more specifically, thyroxine does not reach the cell in its active form.
T4 (thyroxine) is a prohormone. By itself, it has almost no activity at the thyroid hormone receptor. The active form is T3 (triiodothyronine), whose affinity for the nuclear TR receptor is 10–15 times higher than that of T4. T4 → T3 conversion occurs mainly in the periphery.
🌀
Physiology of T4 → T3 conversion
T4 and T3 metabolism is regulated by three deiodinases, each with distinct biology:
▸D1 (type 1) — liver, kidneys. Produces most circulating T3; a selenium-dependent enzyme. ▸D2 (type 2) — brain, pituitary, muscle, brown adipose tissue. Local conversion for tissue T3; selenium-dependent. ▸D3 (type 3) — placenta, skin, fetal brain. Inactivates T4 into rT3 (reverse T3) and T3 into T2 — a “dead-end branch.”
All three deiodinases are selenoproteins. The enzyme active center contains selenocysteine. Without adequate selenium, the enzyme does not assemble or assembles incompletely.
Normal distribution: the thyroid secretes mainly T4 (≈14–17:1 to T3 by weight); about 80% of T3 is formed peripherally, about 20% by the gland itself. Of this T4, peripheral conversion normally produces T3 — 30% (the physiological channel), and rT3 — 40% (physiological inactivation). The rest undergoes excretion and sulfation.
During stress, inflammation, or fasting, D1 activity falls and D3 rises in some tissues: more T4 goes to rT3, less to T3. This is an evolutionary adaptation: during crisis, the body lowers metabolism. But with chronic stress, this switch can remain stuck in “winter” mode for years.
🌀
Where conversion fails: four mechanisms
•Selenium deficiency — deiodinase is a selenoprotein. Serum selenium levels <90 mcg/L are associated with reduced D1 and D2 activity. In regions with selenium-poor soil (Northern Europe, Ukraine, Poland), deficiency is a background state. Our practice orientation: 120–150 mcg/L. •Chronically elevated cortisol — glucocorticoids directly activate D3 and suppress D2 at the transcriptional level. Result: T4 is diverted into the rT3 dead end, tissue T3 falls, and TSH remains normal (because fT4 does not change). Triggers: chronic stress, sleep deprivation <6 h, irregular eating, overtraining. •Ferritin deficiency — TPO (thyroid peroxidase) and conversion itself depend on iron as a cofactor; the direct evidence that iron deficiency lowers their activity comes from animal studies. The 70 ng/mL cut-off is our practice orientation, not a proven threshold: the target in women with hypothyroidism is 70–100 ng/mL, not the “lower limit of normal.” •Systemic inflammation — IL-6, TNF-α, and IL-1β induce D3 and suppress D2. Marker: hsCRP >3 mg/L. Sources: visceral obesity, IBS, leaky gut, chronic infection (EBV, H. pylori), periodontitis, undiagnosed autoimmune disease.
Often all four factors operate in parallel in the same patient. Treating with selenium alone while cortisol remains elevated and ferritin remains low gives only a partial effect — hence “I tried selenium, it did not help.”
🌀
Markers: what to measure besides TSH
Standard screening (TSH + fT4) is blind to functional hypothyroidism. Expanded panel:
| Marker | Our practice orientation |
|---|---|
| TSH | 1.0–2.0 mIU/L |
| fT3 | 4.0–7.0 pmol/L |
| rT3 | 9–24 ng/dL |
| fT3/rT3 | >0.4 (pg/mL : ng/dL) |
| Selenium | 120–150 mcg/L |
| Ferritin (women) | 70–100 ng/mL |
▸TSH (thyroid-stimulating hormone) — our practice orientation is 1.0–2.0 mIU/L on replacement therapy in symptomatic patients. The laboratory reference range (often about 0.4–4.0) is wider; the narrow corridor is our choice, not a guideline requirement. ▸fT4 (free thyroxine) — target upper half of the reference interval (for example, 14–18 pmol/L with a reference range of 9–22). ▸fT3 (free triiodothyronine) — the main marker of tissue activity. Our practice orientation is 4.0–7.0 pmol/L (or 3.5–6.5 with a reference range of 3.1–6.8). In functional hypothyroidism, fT3 is “pressed toward the lower limit.” ▸rT3 (reverse T3) — indicator of “dead-end” conversion. Target 9–24 ng/dL (or 0.14–0.37 nmol/L). >24 ng/dL suggests chronic stress or systemic inflammation. ▸fT3 / rT3 ratio — functional index. The cut-offs are a practice orientation, not a proven cut-off: we read <0.2 with fT3 in pg/mL and rT3 in ng/dL (≈ <20 with pmol/L : nmol/L) as impaired conversion and >0.4 (≈ >40) as preserved conversion. ▸Anti-TPO (thyroid peroxidase antibodies) — the upper reference limit depends on the laboratory method (often about 34–35 IU/mL). Any elevation indicates a Hashimoto background, a common underlying contributor to symptoms. ▸Serum selenium — our practice orientation 120–150 mcg/L. ▸Ferritin — our practice orientation 70–100 ng/mL in women with hypothyroidism, 100–200 in men. ▸Zinc, serum iron, TIBC, transferrin saturation — expanded iron status. ▸Vitamin D 25(OH)D — our practice orientation 60–80 ng/mL. ▸hsCRP — inflammation marker, target <1 mg/L. ▸Morning serum cortisol — to rule out adrenal insufficiency; a diurnal salivary cortisol curve does not make a diagnosis, chronic stress is measured with questionnaires (PSS-10, FSS).
🌀
TPO and Tg antibodies: the background that changes the prognosis
The expanded panel answers what keeps the hormone from working today. Antibodies to thyroid peroxidase (anti-TPO) and thyroglobulin (anti-Tg) answer a different question: where thyroid function is heading over the coming years. They show whether autoimmune thyroiditis (Hashimoto disease) lies behind the hypothyroidism, which changes what to expect from the dose and how often to check it.
- The cut-off depends on the method. The upper limit for anti-TPO is usually about 34–35 IU/mL and for anti-Tg about 115 IU/mL, depending on the laboratory. Read the result against the reference of the laboratory that ran the test.
- Prognosis. In the 20-year follow-up of the Whickham cohort, the odds ratio of developing hypothyroidism in women was 8 with raised TSH alone, 8 with positive antibodies alone and 38 (95% CI 22–65) with both at the first survey; in men it was 44, 25 and 173. In the logit model of the same study, the probability of hypothyroidism rose with TSH above 2 mU/L at the first survey and rose further when antibodies were present (PMID 7641412).
- What it changes on L-thyroxine. In our practice, positive antibodies in a patient on L-thyroxine with normal TSH and fT3 are not a reason to raise the dose or to give glucocorticoids, but a reason to check TSH every 6–12 months and to address cofactors, sleep and possible inflammatory triggers, including celiac disease. The evolution of the antibody background is covered in the four stages of Hashimoto.
- Selenium and antibody titres. In the randomized trial by Gärtner and colleagues in women with autoimmune thyroiditis and anti-TPO above 350 IU/mL, sodium selenite 200 mcg/day for 3 months lowered the mean anti-TPO titre to 63.6% of baseline (about 36%), and by 40% in those starting above 1200 IU/mL (PMID 11932302). The trial used selenite, not selenomethionine.
- When to measure. Once at diagnosis and once when fatigue persists on an adequate dose. Repeat only to assess the response to selenium (at 8–12 weeks and at 6 months) and during and after pregnancy. Re-testing every year without a treatment question does not change management.
- If tachycardia, tremor or weight loss appear on an unchanged dose, TSH-receptor antibodies (TRAb) are needed. If they are positive, an endocrinologist reviews the diagnosis; do not change the dose on your own.
🌀
Holistic protocol for restoring conversion
Principle: repair the enzyme, do not increase the T4 dose. Simply escalating L-thyroxine while the conversion block persists raises rT3 even further — the paradox of “more T4 = less T3.”
1. Selenium — the foundation
▸Selenium (L-selenomethionine) 200 mcg/day in the morning on an empty stomach, for at least 8 weeks, then daily or 5 days per week. ▸Check serum level after 8–12 weeks; our practice orientation is 120–150 mcg/L. ▸In Northern Europe and regions with selenium-poor soil, lifelong nutraceutical supplementation is justified.
2. Iron to target ferritin
▸Iron bisglycinate 25 mg every other day with vitamin C 500 mg for absorption. ▸No dairy, tea, or coffee within ±1 hour of intake. ▸At least 4 hours away from L-thyroxine — iron reduces its absorption; details in iron and thyroid pills. ▸Ferritin 70–100 ng/mL is our practice orientation; monitor every 8 weeks. ▸If oral forms are not tolerated, intravenous iron in an inpatient setting.
3. Zinc, magnesium, vitamin D
▸Zinc (bisglycinate / picolinate) 15–25 mg in the evening — cofactor for T3 synthesis and D1 regulation. ▸Magnesium (glycinate / taurate) 300–400 mg in the evening — thyroid receptor cofactor. ▸Vitamin D3 4000–10000 IU to a level of 60–80 ng/mL, + K2 (MK-7) 100–200 mcg. ▸Iodine is a separate topic; high doses are contraindicated in an autoimmune thyroiditis background. See the article Iodine and thyroid: 5 steps.
4. Lowering cortisol
▸Sleep 7–9 hours, bedtime before 23:00. One hour of sleep loss shifts cortisol by 15–20%. ▸Morning light exposure 10 minutes during the first hour after waking — circadian rhythm reset. ▸Adaptogens (ashwagandha 600 mg) — cortisol normalization and rT3 reduction in small studies. ▸Breathing practices 10 minutes/day — parasympathetic activation. ▸Limit caffeine after 14:00.
5. Reducing systemic inflammation
▸Mediterranean / DASH dietary pattern — olive oil, fish, vegetables, legumes. ▸EPA + DHA 2 g/day — omega-3, IL-6 reduction. ▸Curcumin (liposomal) 500 mg 2×/day — anti-inflammatory. ▸Treatment of hidden infections when confirmed (H. pylori, EBV reactivation, dental caries, periodontitis). ▸Reduction of visceral fat — waist circumference <94 cm (men) / <80 cm (women).
6. When to add T3 directly
▸Liothyronine (L-T3) 5–10 mcg in the morning or split dosing (5 in the morning + 5 at lunch) — discussed with a physician when conversion deficiency is confirmed and symptoms persist for 3–6 months on the full protocol. ▸NDT (natural desiccated thyroid) — T4 + T3 at about 4:1, more T3 than the human thyroid secretes; not recommended by ETA 2012. Details are in the article Hypothyroidism and natural desiccated thyroid (NDT). ▸Check fT3, fT4, TSH after 6–8 weeks after starting T3-containing forms.
🌀
What does NOT work (and why)
▸Blindly increasing the L-thyroxine dose when fT3 is low — more substrate for D3, more rT3, same symptoms. ▸Selenium monotherapy with ferritin 15 ng/mL — without iron repletion the effect is partial. ▸Iodine at >500 mcg/day with selenium deficiency — provokes autoimmune thyroiditis exacerbation through oxidative stress in the thyrocyte. ▸T3 without cortisol correction — risks worsening anxiety and provoking tachycardia. ▸Self-prescribing liothyronine without an expanded panel and monitoring — uncontrolled T3 increases the risk of arrhythmias and osteoporosis. ▸“Normal TSH = thyroid is fine” — in a symptomatic patient with low fT3, this is a working hypothesis of functional hypothyroidism, not a reason to close the case. ▸Vegan / low-protein diet without correction — zinc, iron, B12, and tyrosine deficiency (T4 substrate). Conversion suffers.
🌀
Safety: what not to do without a physician
- Do not stop L-thyroxine on your own, even if cofactors have made you feel better: in overt hypothyroidism withdrawal is dangerous, and in severe forms can lead to myxedema coma.
- Adrenals first. In undiagnosed adrenal insufficiency, starting or raising L-thyroxine can precipitate an adrenal (addisonian) crisis. If this is suspected, cortisol is assessed before the dose is changed, including before adding T3.
- Autoimmune combinations. Hashimoto together with celiac disease and type 1 diabetes, or with adrenal insufficiency (autoimmune polyglandular syndromes), is managed by an endocrinologist.
- Amiodarone, lithium, interferon require a separate approach and are not part of the standard cofactor protocol.
- Selenium. The safe upper limit is 400 mcg/day; chronic excess causes selenosis: brittle hair and nails, garlic odour, peripheral neuropathy.
- Iron. With ferritin above 300 ng/mL iron is not started until the cause is known. Overload thresholds are covered in ferritin and iron overload.
- Vitamin D3. In primary hyperparathyroidism, sarcoidosis and other granulomatous diseases, and familial idiopathic hypercalciuria, the high doses of this protocol are not used; a deficiency is corrected only under serum calcium monitoring, and the decision rests with an endocrinologist; serum calcium is checked at baseline and at 12 weeks.
- Magnesium. Contraindicated in severe renal failure (eGFR below 30 mL/min).
- Ashwagandha. Contraindicated in hyperthyroidism, including transient thyrotoxicosis in autoimmune thyroiditis, and in pregnancy and lactation; it may potentiate benzodiazepines and sedatives.
- Selenium and iodine. In untreated iodine deficiency, high-dose selenium is not given until iodine is corrected; before extending the protocol read iodine and thyroid: 5 steps.
🌀
The other side: L-thyroxine overtreatment
Trying to remove fatigue by raising the L-thyroxine dose is a common iatrogenic error. When TSH falls below the reference range with a normal fT4, the result is subclinical thyrotoxicosis: it adds risks, not energy.
- Heart and mortality. In a pooled individual-data analysis of 10 prospective cohorts (52,674 participants), endogenous subclinical hyperthyroidism (TSH below 0.45 mIU/L with normal fT4) was associated with higher total mortality (HR 1.24), coronary heart disease mortality (HR 1.29) and incident atrial fibrillation (HR 1.68); the risks of coronary death and atrial fibrillation were higher with TSH below 0.10 mIU/L (PMID 22529182). People taking thyroid-altering medication were excluded, so applying this to tablet-induced TSH suppression is an extrapolation, not direct evidence.
- Bone. Subclinical hyperthyroidism is associated with lower bone mineral density and higher fracture risk in postmenopausal women (PMID 28671443).
- When to treat. The ATA and AACE recommend treating subclinical hyperthyroidism with TSH below 0.1 mIU/L in people older than 65 or with heart disease or osteoporosis (PMID 28671443). The exception is TSH suppression prescribed after treatment for differentiated thyroid cancer.
🌀
When to seek care
▸TSH within reference range, fT4 within reference range, but fT3 <4.0 pmol/L (our practice orientation) or in the lower quartile of the reference range. ▸fT3 / rT3 ratio <0.2 with fT3 in pg/mL and rT3 in ng/dL (≈ <20 with pmol/L : nmol/L) — a practice orientation, not a proven cut-off. ▸rT3 >24 ng/dL with normal TSH. ▸Residual hypothyroid symptoms on an adequate L-thyroxine dose for at least 6 months. ▸Suspected functional hypothyroidism without a formal diagnosis — symptomatic subclinical presentation. ▸Hashimoto background + progression of symptoms despite standard therapy. ▸Chronic stress, sleep disturbance, weight gain with a “normal” thyroid panel.
I run an expanded panel (TSH, fT4, fT3, rT3, anti-TPO, anti-Tg, selenium, ferritin, zinc, vitamin D, morning serum cortisol, hsCRP) and create a personalized protocol for restoring conversion — without blindly increasing L-T4.
🌀
The DIO2 Thr92Ala polymorphism: a genetic reason monotherapy fails
Besides the four acquired mechanisms of conversion failure (selenium, cortisol, iron, inflammation), there is an inherited one. The type 2 deiodinase gene (DIO2) carries a common single-nucleotide polymorphism, rs225014, that substitutes alanine for threonine at codon 92 (Thr92Ala). The Ala allele frequency varies with ancestry; in the UK WATTS cohort, 16% of patients on L-T4 were Ala/Ala homozygotes PMID: 19190113.
The substitution does not abolish enzyme function — DIO2 still converts T4 to T3 — but it alters intracellular trafficking. Ala/Ala variant enzyme accumulates in the Golgi apparatus rather than the endoplasmic reticulum, where its physiological substrate is delivered. The result is reduced T3 generation at the tissue level despite normal serum T4 and normal-to-high TSH. Brain tissue, which depends almost entirely on local DIO2 activity for its T3 supply, is the most affected compartment PMID: 28855267.
Clinically, this matters because the standard "TSH-normalized" levothyroxine dose may produce adequate plasma T4 yet leave central nervous system T3 inadequate. In Panicker and colleagues' analysis of the WATTS trial (552 patients on L-T4), Ala/Ala homozygotes had worse baseline well-being on the General Health Questionnaire (GHQ-12) on L-T4 monotherapy and greater improvement on combined L-T4 + L-T3; the polymorphism did not affect serum thyroid hormone levels PMID: 19190113. The authors stated that the result requires replication, and a 2017 review noted that the link between DIO2/MCT10 polymorphisms and preference for combination therapy rests on one small study PMID: 28855267. In thyroidectomized patients on L-T4, carriers of the Ala allele had lower postoperative serum fT3 PMID: 28324063.
Practical implications for the patient who continues to feel hypothyroid on adequate L-T4:
- Genotyping (DIO2 rs225014) is available in most clinical genomics panels and is one-time, inexpensive, and does not require fasting. - The polymorphism does not predict who needs T3; it identifies a population in whom a 3–6 month trial of L-T4 + L-T3 (or NDT) is more likely to produce subjective improvement. - Ala/Ala status should not override fT3 measurement. If fT3 is mid-range or higher and rT3 is suppressed, peripheral conversion is intact regardless of genotype. - Genotype does not change TSH targets, monitoring frequency, or contraindications to T3.
The DIO2 polymorphism explains why two patients with identical TSH, fT4, ferritin and selenium can have divergent symptomatic responses to the same regimen. It is one mechanism — not a substitute for the metabolic workup outlined earlier — but it deserves a place in the diagnostic ladder when fT3 is low and the four acquired causes have been corrected.
🌀
Drugs that inhibit T4→T3 conversion: a pharmacological checklist
Several drugs reproduce the biochemical effect of cortisol on conversion. Drug-induced impairment is common, reversible, and often missed because the patient remains on chronic therapy.
Iopanoic acid, ipodate, and iodinated radiographic contrast. Acutely block DIO1 and DIO2; effect on fT3 lasts 2–4 weeks after a single CT angiography or coronary angiogram. Lab interpretation should be deferred during this window.
Before diagnosing conversion failure as the primary problem, the medication list must be reviewed. Discontinuing or switching a confounding drug — when safe — is faster and more specific than any micronutrient protocol.
🌀
Levothyroxine absorption: what interferes and how to space doses
If TSH stays raised on a formally adequate dose, the first hypothesis is absorption, not deiodinase. It is checked before cofactors are added or the regimen is changed.
- How to take it. L-thyroxine on an empty stomach with water; breakfast and coffee no sooner than 60 minutes later. In the systematic review by Wiesner and colleagues, morning and bedtime dosing were equally effective (PMID 33801406); after changing the schedule, TSH is rechecked at 6–8 weeks.
- Coffee. In a small case series by Benvenga and colleagues, coffee taken with the tablet lowered the T4 area under the curve by 36% in patients and 27% in volunteers and delayed the peak by 38–43 minutes; coffee taken 60 minutes after the tablet did not affect absorption (PMID 18341376).
- Iron, calcium and binding drugs. Iron and calcium supplements, aluminium antacids, sucralfate, cholestyramine and colesevelam reduce L-thyroxine absorption (PMID 24610609, PMID 28153426). They are usually kept at least 4 hours from the tablet; the interval is traditional and has not been tested directly — see iron and thyroid pills.
- Soy and fibre. Soy products reduce absorption (PMID 24610609, PMID 28153426); for fibre the data are mixed — the review by Skelin and colleagues calls its effect not yet fully understood (PMID 28153426). The evidence on food and supplements is limited overall, but every study found pointed toward lower absorption (PMID 33801406); after a major change in diet, TSH is rechecked.
- Gastric acidity and PPIs. The L-thyroxine tablet needs an acidic environment to dissolve. In the study by Centanni and colleagues in patients with multinodular goitre, omeprazole raised TSH in all 10 people on L-thyroxine and the dose had to be raised by 37%; with H. pylori-related or atrophic gastritis the daily L-thyroxine requirement was 22–34% higher (PMID 16641395). On long-term PPIs the dose is reviewed by TSH after 6–8 weeks.
- Celiac disease and other causes of malabsorption. Celiac disease, atrophic gastritis, H. pylori, lactose intolerance, inflammatory bowel disease and bariatric surgery impair L-thyroxine absorption (PMID 33708175). In autoimmune thyroiditis with an unexplained rising dose, celiac disease is tested: tissue transglutaminase antibodies (tTG-IgA) together with total IgA.
- Liquid form and soft-gel capsules. They need no acid to dissolve. In the review by Fallahi and colleagues, the liquid form bypasses malabsorption with raised gastric pH and after bariatric surgery and keeps TSH better controlled in celiac disease and lactose intolerance (PMID 33708175). It is used when TSH stays raised on an adequate tablet dose in a patient with one of these causes.
- Biotin. High-dose biotin (5 mg/day or more, popular “for hair”) distorts some immunoassays for TSH, fT4 and fT3; it is stopped at least 48 hours before the blood test.
🌀
Liothyronine pharmacokinetics and a stepwise titration protocol
Half-life, peak timing and titration decide whether liothyronine helps or causes palpitations and tremor.
Oral liothyronine is rapidly and almost completely absorbed (bioavailability ~95%). Peak serum T3 occurs 2–4 hours after ingestion, with the post-dose Cmax frequently exceeding the upper reference limit even at therapeutic doses. The elimination half-life is approximately 20–24 hours, but the biological half-life — the duration of receptor occupancy — is shorter, which is why a single morning dose produces visible serum oscillation and symptomatic swings PMID: 23072197.
Practical consequences:
- A single morning 10 mcg dose produces a supraphysiologic peak at 09:00–11:00 and a trough by the next morning. Split dosing (2.5–5 mcg twice daily) attenuates the peak and provides smoother coverage. - Trough fT3 (drawn before the next dose) is the only meaningful monitoring value. Peak fT3 (drawn 2–4 hours after dosing) is uninterpretable because it captures the absorption surge, not the steady state. - Starting dose in a patient already on adequate L-T4 with low fT3: 2.5–5 mcg in the morning, with a parallel reduction of L-T4 by 12.5–25 mcg to keep TSH stable. The conversion-equivalence is roughly 1 mcg T3 ≈ 3 mcg T4. - Titrate at 4–6 week intervals using TSH, fT4, and pre-dose fT3. Target: TSH within reference, fT3 in the upper third of reference, fT4 mid-reference or slightly below.
In the 2024 LEVOLIO randomized trial, L-T4 + L-T3 was no better than L-T4 alone for quality of life or tissue markers, and patients showed no preference for it PMID: 38124252; in a meta-analysis of 11 randomized trials, by contrast, patients preferred the combination more often than L-T4 alone (52% vs 24%) PMID: 39290156. T3 therapy is therefore an n-of-1 trial with defined start, stop, and monitoring criteria, not a long-term default.
🌀
Why low T3 matters: outcomes data beyond symptoms
Low fT3 has outcome data beyond symptoms: it is a measured prognostic marker in several non-thyroid conditions.
In chronic heart failure, fT3 below the lower reference limit is an independent predictor of all-cause and cardiovascular mortality after adjustment for ejection fraction, NT-proBNP, and NYHA class. In the Pisa cohort of cardiac patients, low fT3 was the most important predictor of death at one year (cardiac deaths 7.5% vs 1.5%) PMID: 12578873, and a meta-analysis of 41 studies in cardiovascular patients found a hazard ratio of 2.06 for cardiac death with non-thyroidal illness syndrome PMID: 27776249.
In acute myocardial infarction, low admission T3 correlates with infarct size, lower left ventricular ejection fraction at discharge, and higher 1-year mortality. The mechanism is presumed to be reduced cardiomyocyte T3 signaling at a time of maximal repair demand.
In critical illness, low T3 with normal or low TSH is the hallmark of non-thyroidal illness syndrome. Mortality in ICU populations rises with the magnitude of fT3 suppression. This is associated, not causal — replacing T3 in unselected critically ill patients has not improved survival in randomized trials, and current consensus is observation, not treatment PMID: 33320308.
In obesity and metabolic syndrome the pattern is different: euthyroid people with obesity have higher TSH, fT3 and fT3/fT4 ratios than people without obesity, and deiodinase function in adipose tissue is altered PMID: 38201918.
Two points for the ambulatory patient:
- A low-normal fT3 in a euthyroid patient with cardiovascular disease, diabetes, or unexplained fatigue is not a benign finding. It does not automatically mandate T3 replacement, but it does identify a population worth investigating for the four acquired conversion causes already discussed. - The outcome data refer to spontaneous low T3, not iatrogenic low T3 from levothyroxine monotherapy. Whether correcting iatrogenic low T3 with combined therapy improves cardiovascular outcomes is an open question; trials have measured symptoms and weight, not mortality.
🌀
Differential diagnosis: impaired conversion versus three look-alikes
The phrase "functional hypothyroidism" risks being applied to any patient with a low fT3, including patients whose physiology is entirely different. Four entities share the biochemical pattern of low or low-normal fT3, and each has a different management.
1. Impaired peripheral conversion (the subject of this article). TSH normal, fT4 normal or high-normal, fT3 low, rT3 high, fT3/rT3 ratio reduced. Ferritin, selenium, zinc, hsCRP, cortisol provide the mechanistic explanation. Treatment: correct deficiencies; consider T3 trial if symptoms persist.
2. Non-thyroidal illness syndrome (sick euthyroid). Acute or chronic systemic illness, often with measurable inflammation (hsCRP elevated, ferritin sometimes elevated as an acute-phase reactant). TSH may be low, normal, or transiently elevated during recovery. fT4 typically low-normal, fT3 low, rT3 high. Fasting reproduces a similar pattern as an adaptive response — serum T3 falls and rT3 rises, and both return to baseline within about 5 days of refeeding PMID: 1150863. Treatment: the underlying illness, not thyroid hormone PMID: 33320308.
A pragmatic decision rule:
- Low fT3 + low fT4 + low or low-normal TSH → think central hypothyroidism, request pituitary workup. - Low fT3 + normal fT4 + normal TSH + acute illness → think non-thyroidal illness, treat the illness. - Low fT3 + normal fT4 + normal TSH + chronic symptoms + high rT3 + nutrient/cortisol abnormality → impaired conversion. - High fT3 and fT4 with non-suppressed TSH → think resistance, refer to endocrinology.
Selenium supplementation has been shown to reduce TPO-antibody titers in Hashimoto thyroiditis in several randomized trials PMID: 38243784, PMID: 33650299, but it does not treat any of the four entities above by itself. It corrects one of several conversion cofactors; the rest of the differential still applies.
The diagnostic separation is not academic. The patient with central hypothyroidism started on T3 without cortisol assessment can precipitate an adrenal crisis. The patient with non-thyroidal illness given thyroid hormone can develop arrhythmia without any benefit. The patient with resistance treated as conversion failure receives medication that worsens the resistance state. Functional hypothyroidism is a real entity but a residual diagnosis — made after the alternatives have been excluded, not before.
🌀
Conclusion
T4 is a prohormone. The active hormone is T3. The conversion enzyme — deiodinase — is a selenoprotein; iron and zinc support thyroid hormone metabolism (deiodinase data mostly from animals). The enzyme works under conditions of normal cortisol and low inflammation.
When any of these four conditions is disrupted, the patient enters functional hypothyroidism: TSH is normal, fT4 is normal, fT3 is low, and symptoms persist. This is visible on the expanded panel and invisible on the standard panel.
Treatment is directed not at the L-T4 dose, but at restoring the conditions required for the enzyme to work: selenium, iron, zinc, vitamin D, cortisol reduction, inflammation reduction, and, when needed, adding T3 or NDT. One measured fT3 can spare the dose escalation.
🌀
Sources
▸Bianco AC, et al. Paradigms of dynamic control of thyroid hormone signaling. Endocr Rev 2019;40:1000–1047. PMID 31033998 ▸Köhrle J. Selenium and thyroid. Best Pract Res Clin Endocrinol Metab 2009;23:815–827. PMID 19942156 ▸Wajner SM, Maia AL. New insights toward the acute non-thyroidal illness syndrome. Front Endocrinol 2012;3:8. PMID 22654851 ▸Salvatore D, et al. Thyroid hormones and skeletal muscle — new insights and potential implications. Nat Rev Endocrinol 2014;10:206–214. PMID 24322650 ▸Wiersinga WM. T4 + T3 combination therapy: an unsolved problem of increasing magnitude and complexity. Endocrinol Metab (Seoul) 2021;36:938–951. PMID 34587734 ▸Toulis KA, et al. Selenium supplementation in autoimmune thyroiditis. Thyroid 2010;20:1163–1173. PMID 20883174 ▸Mancini A, et al. Thyroid hormones, oxidative stress, and inflammation. Mediators Inflamm 2016;6757154. PMID 27051079 ▸Jonklaas J, et al. Guidelines for the treatment of hypothyroidism: prepared by the American Thyroid Association task force on thyroid hormone replacement. Thyroid 2014;24:1670–1751. PMID 25266247 ▸Garber JR, et al. Clinical practice guidelines for hypothyroidism in adults: cosponsored by AACE and ATA. Thyroid 2012;22:1200–1235. PMID 22954017 ▸Hoermann R, et al. Recent advances in thyroid hormone regulation: toward a new paradigm for optimal diagnosis and treatment. Front Endocrinol 2017;8:364. PMID 29375474 ▸Saravanan P, et al. Psychological well-being in patients on 'adequate' doses of L-thyroxine. Clin Endocrinol 2002;57:577–585. PMID 12390330 ▸Vanderpump MP, et al. The incidence of thyroid disorders in the community: a twenty-year follow-up of the Whickham Survey. Clin Endocrinol 1995;43:55–68. PMID 7641412 ▸Gärtner R, et al. Selenium supplementation in patients with autoimmune thyroiditis decreases thyroid peroxidase antibodies concentrations. J Clin Endocrinol Metab 2002;87:1687–1691. PMID 11932302 ▸Nygaard B, et al. Effect of combination therapy with thyroxine (T4) and triiodothyronine versus T4 monotherapy in patients with hypothyroidism. Eur J Endocrinol 2009;161:895–902. PMID 19666698 ▸Carlé A, et al. Hypothyroid patients encoding combined MCT10 and DIO2 gene polymorphisms may prefer L-T3 + L-T4 combination treatment. Eur Thyroid J 2017;6:143–151. PMID 28785541 ▸Benvenga S, et al. Altered intestinal absorption of L-thyroxine caused by coffee. Thyroid 2008;18:293–301. PMID 18341376 ▸Ianiro G, et al. Levothyroxine absorption in health and disease, and new therapeutic perspectives. Eur Rev Med Pharmacol Sci 2014;18:451–456. PMID 24610609 ▸Skelin M, et al. Factors affecting gastrointestinal absorption of levothyroxine: a review. Clin Ther 2017;39:378–403. PMID 28153426 ▸Wiesner A, et al. Levothyroxine interactions with food and dietary supplements — a systematic review. Pharmaceuticals 2021;14:206. PMID 33801406 ▸Fallahi P, et al. L-T4 therapy in enteric malabsorptive disorders. Front Endocrinol 2021;12:626371. PMID 33708175 ▸Centanni M, et al. Thyroxine in goiter, Helicobacter pylori infection, and chronic gastritis. N Engl J Med 2006;354:1787–1795. PMID 16641395 ▸Collet TH, et al. Subclinical hyperthyroidism and the risk of coronary heart disease and mortality. Arch Intern Med 2012;172:799–809. PMID 22529182 ▸Donangelo I, Suh SY. Subclinical hyperthyroidism: when to consider treatment. Am Fam Physician 2017;95:710–716. PMID 28671443 ▸Wiersinga WM, et al. 2012 ETA Guidelines: the use of L-T4 + L-T3 in the treatment of hypothyroidism. Eur Thyroid J 2012;1:55–71. PMID 24782999
Related articles: Iodine and thyroid: 5 steps, Hypothyroidism and natural desiccated thyroid (NDT).
🌀
FAQ
Can thyroid function be assessed by TSH alone? No, not if symptoms are present. TSH is a marker of pituitary feedback, not tissue activity. Patients with residual symptoms on L-T4 need an expanded panel: fT4, fT3, rT3, anti-TPO, anti-Tg, selenium, ferritin, vitamin D, morning serum cortisol.
What should be done if fT3 is low while TSH and fT4 are normal? This is a working hypothesis of functional hypothyroidism. Algorithm: check selenium, ferritin, zinc, vitamin D, morning serum cortisol, hsCRP. Correct identified deficiencies. After 8–12 weeks, repeat the expanded panel. If fT3 has not increased and symptoms remain, discuss T3 or NDT with a physician.
Is rT3 dangerous by itself? rT3 is biologically inactive, but high rT3 is a marker of “winter” mode: chronic stress, inflammation, fasting, severe illness. rT3 falls in parallel with cortisol and hsCRP reduction — it is not treated in isolation.
When should T3 (liothyronine) or NDT be tried? After 3–6 months on the full protocol (selenium, iron, vitamin D, zinc, cortisol reduction) if low fT3 and symptoms persist. Starting low-dose T3 (5 mcg in the morning) or switching to NDT should be done only under physician supervision, with expanded panel monitoring after 6–8 weeks.
This article is for informational purposes and does not replace medical consultation. Before starting any nutraceuticals, changing medication therapy, or undergoing diagnostic procedures, discuss the plan with your treating physician.
Key facts
- T4 (thyroxine) is a prohormone; the active form T3 has 10–15 times higher receptor affinity.
- Deiodinases D1 and D2 convert T4 to T3, while D3 inactivates the hormone; all three are selenoproteins.
- By the 2012 ETA estimate, 5–10% of patients on a TSH-adequate L-thyroxine dose keep hypothyroid symptoms.
- Functional hypothyroidism: normal TSH and fT4 but low fT3 with persisting symptoms.
- Ferritin of 70–100 ng/mL in women with hypothyroidism is our practice orientation, not a target from clinical guidelines.

