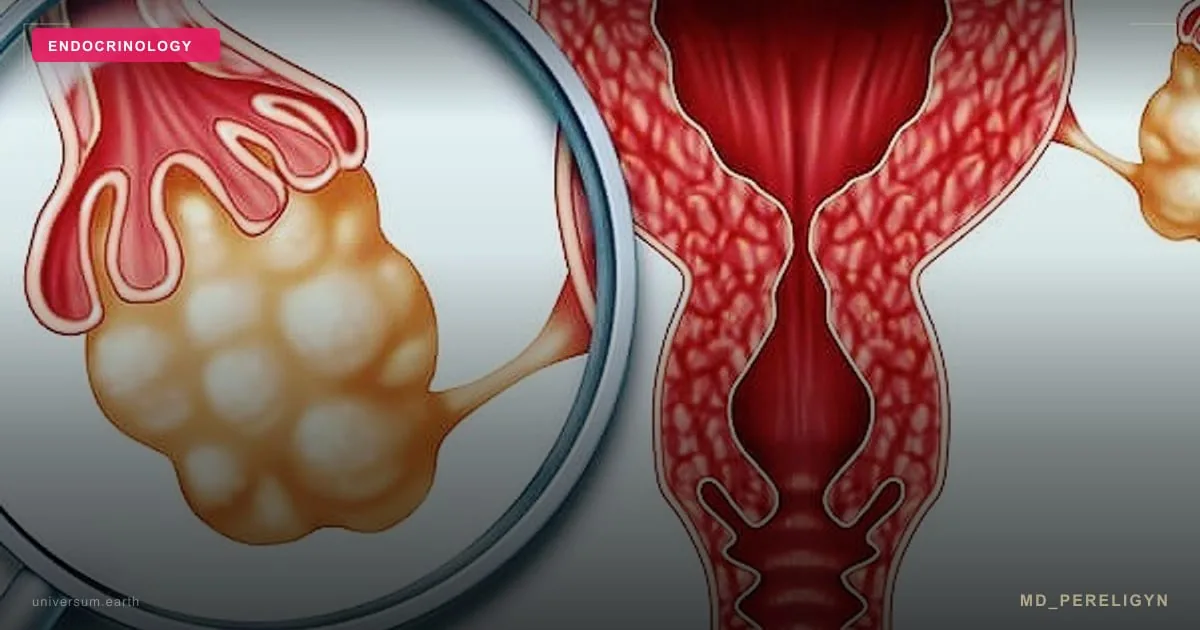
in pictures and a few words
What it is and how it’s diagnosed
PCOS is polycystic ovary syndrome, the most common hormonal disorder in women of childbearing age. It is diagnosed by 2 of 3 signs, after tests rule out similar conditions.
- Irregular periods (in adults, a cycle shorter than 21 or longer than 35 days) or none
- Too many male hormones: acne, excess hair, hair loss — or on a blood test
- Many small bubbles in the ovary on ultrasound or a special test; not counted in teens
Where insulin comes in
In most women with PCOS, cells respond less well to insulin — the hormone that lowers sugar. This happens even at a normal weight.
- Extra insulin makes the ovaries produce more male hormones
- This is a key mechanism, but not the only one
- A fasting insulin test and calculations based on it are not advised in routine practice
Birth control pills
Hormonal birth control pills are the first medicine for irregular periods and excess male hormones in adults. Symptoms usually return after stopping them.
- Lower male hormones, even out the cycle, reduce acne and excess hair
- Protect the uterine lining from overgrowth
- Don’t fix the insulin problem: sugar, weight, blood pressure and blood fats are checked separately
Metformin and spironolactone
Metformin helps insulin work. The doctor raises the dose gradually; if needed, it is added to birth control pills.
- Spironolactone reduces acne and excess hair; the effect comes after 3–6 months
- On spironolactone, reliable protection from pregnancy is a must
- They can be combined: together they often work better than separately
Food and movement
No special diet is needed: any balanced eating you can keep up long-term will do. With excess weight — with a moderate calorie deficit.
- 150 minutes of moderate activity and 2 strength workouts a week
- With excess weight, even moderate weight loss noticeably improves the cycle and metabolism
- At a normal weight, the focus is on strength training 2–3 times a week
Inositol and other supplements
Inositol is sold without a prescription and bothers the stomach and gut less often than metformin. The guideline considers it experimental: benefit is shown for some metabolic measures.
- The decision to try inositol is made together with a doctor
- For vitamin D, omega-3, berberine and other supplements, evidence of benefit is insufficient
- Tell your doctor about any supplement: some interact with medicines
If you want a baby
You can get pregnant with PCOS. With excess weight, weight loss often restores egg release on its own.
- The first medicine to trigger egg release is letrozole; metformin — when indicated
- Spironolactone is stopped a month before a planned pregnancy
Regular check-ups
PCOS raises the risk of type 2 diabetes, high blood pressure, heart and blood vessel disease, overgrowth of the uterine lining and uterine cancer, and depression. Follow-up is needed even if pregnancy isn’t planned.
- Fasting sugar and 2 hours after a sweet drink — at diagnosis and every 1–3 years
- Blood pressure — at every visit; blood fats — every 1–2 years; waist — every six months
- Snoring, unrefreshing sleep, daytime sleepiness — tell your doctor
Who should see a doctor first
Blood sugar repeatedly below 3.0 mmol/L (54 mg/dL) or above 8.9 mmol/L (160 mg/dL) — see a doctor.
- No periods for a long time, bleeding between them or unusual bleeding — don’t delay an exam and ultrasound
- Metformin: B12 at the start, after a year, then yearly from 1500 mg a day or after 4 years
- Spironolactone: potassium and a kidney test at the start, after 4–6 weeks, then every 6–12 months
Important. Potassium is checked more often with weaker kidneys, certain blood pressure medicines, anti-inflammatory painkillers or a potassium-rich diet.
In one sentence
Even on the pill, the insulin problem remains. That’s why PCOS calls for good food, movement, regular sugar checks and, if needed, metformin.
The Most Common Endocrine Disorder in Women
Polycystic ovary syndrome (PCOS) affects 8-13% of reproductive-age women, making it the most prevalent endocrine disorder in women (Bozdag et al., Human Reproduction Update, 2016). Up to 70% of cases remain undiagnosed. The average time from symptom onset to diagnosis exceeds 2 years, with patients seeing an average of 3 physicians before receiving the correct diagnosis.
Rotterdam Criteria: Establishing the Diagnosis
PCOS is diagnosed when at least 2 of 3 criteria are present (Rotterdam Consensus, 2003; thresholds refined in the 2023 international guideline [PMID: 37580314[1]]):
1. Oligo-ovulation or anovulation — irregular cycles (in adults: cycles <21 or >35 days, fewer than 8 cycles per year, or any cycle >90 days) or amenorrhea 2. Clinical and/or biochemical hyperandrogenism — acne, hirsutism, alopecia, elevated free testosterone or DHEA-S 3. Polycystic ovarian morphology on ultrasound — 20 or more follicles measuring 2-9 mm in at least one ovary (transvaginal, transducer ≥8 MHz) and/or ovarian volume ≥10 mL; in adults, elevated AMH can be used instead of ultrasound, while in adolescents neither ultrasound nor AMH is used for diagnosis
Important: other causes of hyperandrogenism must be excluded — congenital adrenal hyperplasia (17-OH progesterone), prolactinoma (prolactin), hypothyroidism (TSH); when clinical features suggest them, Cushing syndrome (cortisol) and androgen-secreting tumours.
Insulin Resistance: A Key Mechanism, but Not the Only One
Insulin resistance is present in 70-80% of women with PCOS (both obese and lean). The mechanism: excess insulin stimulates ovarian theca cells to overproduce androgens (testosterone, androstenedione) and reduces SHBG, increasing bioavailable free testosterone.
How glucose metabolism is assessed in PCOS: - Glycaemic status is checked in everyone at diagnosis and every 1–3 years thereafter (more often with other diabetes risk factors). The most accurate test is the 75 g OGTT (glucose at 0 and 120 minutes), regardless of weight; if it cannot be done, fasting glucose and/or HbA1c, which are notably less accurate. When planning pregnancy or seeking fertility treatment, an OGTT is offered to everyone without diabetes [PMID: 37580314[1]]. - Fasting insulin and HOMA-IR — not recommended by the 2023 guideline in routine practice: results depend on the assay and treatment decisions are not based on them [PMID: 37580314[1]] - If glucose is repeatedly below 3.0 mmol/L (54 mg/dL) or above 8.9 mmol/L (160 mg/dL) — see a doctor.
| Marker | What the 2023 guideline says |
|---|---|
| 75 g OGTT (glucose 0 and 120 min) | most accurate test; at diagnosis and every 1-3 years |
| Fasting insulin, HOMA-IR | not recommended in routine practice: cut-offs are not standardised |
| AMH | in adults, an alternative to ultrasound; cut-off is assay-specific, no single number |
Anti-Mullerian Hormone (AMH): A PCOS Biomarker
AMH is produced by granulosa cells of preantral and small antral follicles. In PCOS, AMH is usually elevated 2-3 fold due to the large number of immature follicles. Dewailly et al. (Human Reproduction Update, 2014) proposed AMH as an additional diagnostic criterion. The 2023 guideline accepts AMH in adults as an alternative to ultrasound for ovarian morphology, but not as a stand-alone test: there is no single cut-off, as it depends on the laboratory assay. AMH is not used for diagnosis in adolescents [PMID: 37580314[1]].
Why Birth Control Alone Is Not Enough
Combined oral contraceptives (COCs) are the first-line medical therapy for irregular cycles and hyperandrogenism in adults under the 2023 guideline [PMID: 37580314[1]]. They suppress ovarian androgens, regulate cycles, improve acne and hirsutism, and protect the endometrium.
However, COCs do not address insulin resistance or lower metabolic risk, so glucose status, weight, blood pressure, and lipids are assessed separately, and metformin can be added to a COC when needed. The guideline does not favour any specific COC formulation and advises the lowest effective oestrogen dose. After stopping COCs, the symptoms they controlled usually return: PCOS is a chronic condition.
Comprehensive PCOS Treatment Protocol
1. Inositol (Myo-inositol + D-chiro-inositol)
Myo-inositol (MI) is a second messenger in insulin signaling. MI deficiency is thought to contribute to insulin resistance in PCOS. However, the 2023 guideline classifies inositol as an experimental therapy. The meta-analysis prepared for the guideline (Fitz et al., JCEM, 2024; 30 trials) found benefit of myo- or D-chiro-inositol for some metabolic measures and possible benefit of D-chiro-inositol for ovulation; for other outcomes an effect was not shown, and no dose or ratio (including 40:1) has been shown to be superior [PMID: 38163998[2]]. A decision to try inositol is made with the doctor, with the limited evidence in mind.
2. Metformin
An insulin sensitizer that reduces hepatic glucose production. Cochrane meta-analysis (Morley et al., 2017): metformin improves ovulation, reduces androgens, and decreases weight in PCOS. Starting dose: 500 mg, titrated to 1,500-2,000 mg/day.
3. Spironolactone
An aldosterone antagonist with anti-androgenic activity. Blocks androgen receptors and inhibits 5-alpha reductase. Dosage: 50-200 mg/day. Effects on acne and hirsutism appear after 3-6 months. Contraception is mandatory (teratogenic risk).
4. Lifestyle Management
Frequently Asked Questions
Can you get pregnant with PCOS? Yes. In women with excess weight, weight loss alone often restores ovulation. The first-line drug for ovulation induction is letrozole (in a 2014 NEJM randomised trial it gave more live births than clomiphene); metformin is used when indicated [PMID: 37580314[1]].
Is PCOS permanent? PCOS is a chronic condition with genetic predisposition. However, symptoms can be controlled and minimized with treatment matched to the dominant features.
Should PCOS be treated if pregnancy is not planned? Yes, at least with monitoring. PCOS increases the risk of type 2 diabetes (about threefold: RR 3.00 in a meta-analysis of cohort studies [PMID: 32995872[3]]), cardiovascular disease, endometrial hyperplasia and cancer, depression, and metabolic syndrome.
How does inositol compare with metformin? Inositol causes fewer GI side effects and needs no prescription, but its evidence base is weaker: the 2023 guideline considers it experimental. In the meta-analysis metformin reduced hirsutism and waist-hip ratio more; for reproductive outcomes there is likely no difference [PMID: 38163998[2]]. A benefit of combining both has not been shown.
This article is for educational purposes only and does not constitute medical advice. Always consult a qualified healthcare professional before starting any treatment.
🌀
Rotterdam Phenotypes: Four Subgroups Under One Diagnosis
The Rotterdam consensus defines PCOS by any two of three criteria, which mathematically yields four phenotypes. The 2023 International Evidence-Based Guideline endorses phenotype-specific risk stratification because metabolic burden differs substantially across subgroups.
Phenotype A (classic/full PCOS) combines hyperandrogenism, oligo-anovulation, and polycystic ovarian morphology. This is the most metabolically severe form. Prevalence of insulin resistance and metabolic syndrome is highest here.
Phenotype B has hyperandrogenism and oligo-anovulation without polycystic ovarian morphology on ultrasound. Metabolic risk approaches phenotype A. Patients in this group are frequently misdiagnosed as "not PCOS" because of normal-appearing ovaries on imaging, even though insulin resistance, dyslipidaemia, and androgen excess are fully present.
Phenotype C (ovulatory PCOS) combines hyperandrogenism with polycystic ovarian morphology but preserved regular ovulation. Metabolic risk is intermediate. Cycles are present, fertility may be normal, but acne, hirsutism, and androgenic alopecia drive clinical presentation. Spironolactone and combined oral contraceptives remain first-line; metformin is added for metabolic features found on OGTT, fasting glucose, or HbA1c (the 2023 guideline does not recommend fasting insulin or HOMA-IR cut-offs in routine practice), while inositol remains experimental [PMID: 38163998[2]].
Phenotype D (non-hyperandrogenic PCOS) combines oligo-anovulation with polycystic ovarian morphology but without clinical or biochemical hyperandrogenism. Metabolic risk is lowest and closest to controls. Some authors question whether phenotype D represents a distinct disorder from functional hypothalamic anovulation; differentiation requires ruling out energy deficit, hyperprolactinaemia, and thyroid dysfunction.
Clinical implication: insulin-targeted therapy (metformin, GLP-1 agonists) yields the largest absolute benefit in phenotypes A and B. Androgen-targeted therapy (spironolactone, combined oral contraceptives, finasteride) gives proportionally larger benefit in phenotype C. Phenotype D often responds to weight restoration and behavioural changes alone. Documenting the phenotype at diagnosis allows the patient and clinician to focus the therapeutic protocol rather than apply a generic PCOS template, and aligns laboratory follow-up with the dominant pathology — glycaemic status (OGTT, fasting glucose, or HbA1c) every 1-3 years for phenotypes A-B, free testosterone and SHBG for phenotype C, and cycle tracking with bone-density review for phenotype D when amenorrhoea persists.
🌀
Letrozole Protocol for Ovulation Induction
Letrozole, an aromatase inhibitor, replaced clomiphene citrate as the first-line ovulation induction agent in PCOS based on the 2014 NIH Pregnancy in Polycystic Ovary Syndrome II (PPCOS II) trial, which demonstrated higher live-birth rates (27.5% vs 19.1%) and higher cumulative ovulation rates with letrozole. The 2023 international guideline now lists letrozole as recommended first-line and clomiphene as alternative.
🌀
Endometrial Protection and Surveillance
Chronic anovulation produces unopposed oestrogen exposure of the endometrium. Without periodic progestin opposition, the endometrium undergoes proliferation, then complex hyperplasia, then in some patients endometrial carcinoma. Women with PCOS have an increased risk of endometrial carcinoma compared with women without PCOS (OR 2.79; 95% CI 1.31–5.95) [PMID: 24688118[4]].
Progestin regimens (when contraception is not desired). Cyclic micronised progesterone 200 mg orally at bedtime for 12-14 days every 1-3 months induces a predictable withdrawal bleed. Medroxyprogesterone acetate 10 mg daily for 10-14 days is an alternative. The levonorgestrel-releasing intrauterine system (52 mg, 8-year duration) provides continuous endometrial protection and is a long-term option for patients with abnormal uterine bleeding plus anovulatory PCOS.
🌀
Adolescent PCOS: Why Adult Criteria Misclassify
Adolescent PCOS diagnosis is the most frequent source of overdiagnosis in endocrine practice. The Rotterdam ultrasound criterion (originally 12+ follicles 2-9 mm, now 20+ per ovary under the 2023 guideline; ovarian volume ≥10 mL) overlaps almost completely with normal post-menarchal ovarian appearance, where multifollicular ovaries are physiological for 2-3 years after first menses.
The 2017 international adolescent PCOS criteria, reaffirmed in 2023, require both persistent oligo-anovulation and clinical or biochemical hyperandrogenism, and explicitly exclude ultrasound from the diagnostic criteria within eight years of menarche [PMID: 37580314[1]].
References
- thresholds refined in the 2023 international guideline []. PMID 37580314
- PMID 38163998
- PMID 32995872
- PMID 24688118
Key facts
- Diagnosis needs 2 of 3 Rotterdam criteria: oligo/anovulation, hyperandrogenism, polycystic morphology (20+ follicles in one ovary or volume ≥10 mL; in adults, elevated AMH can replace ultrasound).
- Insulin resistance affects 70-80% of women with PCOS and is a key but not the only mechanism; excess insulin drives ovarian androgens and lowers SHBG.
- The 2023 guideline does not recommend fasting insulin or HOMA-IR in routine practice: there are no reliable cut-offs. Glycaemic status is checked in everyone at diagnosis: the most accurate test is the 75 g OGTT; fasting glucose and/or HbA1c are used if an OGTT cannot be done and are notably less accurate.
- The 2023 guideline regards inositol as experimental: benefit is shown for some metabolic measures, while for most other outcomes an effect has not been shown.
- COCs are first-line for irregular cycles and hyperandrogenism in adults but do not address insulin resistance; metabolic risk is assessed separately.




