in pictures and a few words
What it is and why it matters
Daridorexant is a new type of sleeping pill for adults with insomnia. It does not dull the brain — it removes the wake-up signal.
- Helps when it is hard to fall asleep or hard to stay asleep
- It does not press the brain’s brake — it lets go of the accelerator
What keeps us awake
There is a small group of nerve cells in the brain. They release orexin — a substance that keeps the wakefulness system switched on.
- It supports the centres responsible for attention and alertness
- There is a disease in which these cells die — and a person falls asleep in the middle of the day
- So orexin is not a guess but a well-studied switch
How the pill works
The medicine temporarily occupies the spots where orexin attaches. The wake-up signal weakens and sleep comes by itself — without suppressing the brain.
- The effect is temporary and reversible
Unlike usual sleeping pills
Usual sleeping pills strengthen the brain’s brake and dull it as a whole. Daridorexant acts precisely — only on the wake-up signal.
- Less grogginess in the morning: by the time you get up, the medicine is mostly cleared
- Less effect on coordination and the risk of falls
- The risk of dependence is lower than with usual sleeping pills, but it exists
What the studies showed
The medicine was compared with a dummy pill in people with insomnia. With it, people fell asleep faster and spent less time awake after falling asleep.
- Sleep was measured with devices, not only from what people said
- At the 50 mg dose people also felt better during the day
Tested in people. Tested in people with insomnia: sleep was better than on a dummy pill, and at 50 mg so was how people felt during the day.
How to take it
Usually 50 mg 30 minutes before bed, once a night, and only if at least 7 hours of sleep lie ahead. 25 mg only if the doctor decides so.
- Not again in the middle of the night or in the morning
- After a heavy, fatty dinner it will start working later
What you may feel
Most often — headache and sleepiness during the day.
- Rarely: sleep paralysis, vivid images when falling asleep, muscle weakness with emotions
- This is reversible and usually goes away after stopping
- With alcohol and other substances that depress the nervous system — dangerous
The main treatment needs no pills
For chronic insomnia, the first step is not a pill but work on sleep habits. Its benefit lasts after the course, while a pill helps only as long as you take it.
- A regular sleep and wake schedule
- Not spending extra time in bed
- Breaking the learned link “bed — anxiety”
Who should see a doctor first
First, the cause of insomnia is sorted out: pauses in breathing during sleep, restless legs, depression and anxiety, pain, night work, caffeine and alcohol.
- Not for the disease in which a person suddenly falls asleep in the middle of the day
- Caution: severe pauses in breathing during sleep, chronic lung disease, older age
- Not recommended in severe liver disease
Important. If you need to get up at night and stay steady on your feet, discuss it with a doctor. How long to take it is decided in advance, not extended out of habit.
In one sentence
Daridorexant helps you fall asleep by removing the wake-up signal, not by dulling the brain. But the main treatment for insomnia is sleep habits, and the pill is support for a while.
In brief
How the brain keeps itself awake
The hypothalamus contains a small group of neurons that produce orexin (also known as hypocretin). Its function is to keep the wakefulness system switched on, sustaining the centres responsible for attention and arousal.
What happens without orexin is precisely known: in narcolepsy those neurons die, people fall asleep in the middle of the day and lose muscle tone with emotion. Orexin is therefore not a hypothesis but a well-described switch.
Hence the idea: occupy orexin receptors temporarily and reversibly, the wakefulness signal weakens, and sleep arrives on its own — without suppressing the brain.
How this differs from familiar hypnotics
| Zolpidem, benzodiazepines | Daridorexant | |
|---|---|---|
| Target | GABA system (the brain's main brake) | Orexin receptors (the wakefulness system) |
| Principle | Amplify inhibition | Remove the wakefulness signal |
| Effect on the brain | General suppression of activity | Selective release of "hold" |
| Morning grogginess | Characteristic | Less |
| Coordination, falls | A significant problem, especially in older people | Less pronounced |
| Dependence and withdrawal | Marked | Milder, though the class is controlled |
What the trials showed
▸Two randomised phase 3 trials (Lancet Neurology, 2022). Daridorexant improved objective polysomnographic measures — reducing latency to sleep onset and wake after sleep onset — at 25 and 50 mg, and at 50 mg also self-reported daytime functioning [1].
The second point matters more than it appears. Many hypnotics extend sleep in the laboratory without improving the day. It is the day — capacity, attention, wellbeing — that concerns the patient.
Dosing and rules
| Parameter | Detail |
|---|---|
| Dose | 25 mg or 50 mg |
| When | 30 minutes before bed |
| Frequency | Once per night; repeat dosing is not acceptable |
| Condition | At least 7 hours available for sleep |
| Food | Fatty meals delay onset |
The standard dose is 50 mg. 25 mg is used at the clinician's discretion, including in moderate hepatic impairment and with moderate CYP3A4 inhibitors (erythromycin, ciprofloxacin, ciclosporin) [3].
Safety
▸Common: headache, daytime sleepiness. ▸Rare but class-specific: sleep paralysis, vivid imagery on falling asleep or waking, brief muscle weakness with emotion. Reversible. ▸Contraindications: narcolepsy; concomitant strong CYP3A4 inhibitors (itraconazole, clarithromycin, ritonavir) [3]. ▸Caution: severe sleep apnoea, chronic lung disease, older age, any need to get up at night with intact coordination. ▸Liver: not recommended in severe impairment. ▸Alcohol and other CNS depressants — a dangerous combination. ▸Status: controlled substance (Schedule IV in the US); abuse potential lower than classic hypnotics but not zero.
Where it belongs in treating insomnia
It is important not to be seduced by mechanistic novelty. In chronic insomnia, first line remains cognitive behavioural therapy: work on the sleep-wake schedule, restriction of time in bed, and breaking the learned association between bed and anxiety. Its effect persists after the course ends — something no hypnotic offers.
A sensible sequence looks like this:
▸identify the cause: sleep apnoea, restless legs, depression and anxiety, pain, night work, caffeine and alcohol; ▸begin cognitive behavioural work; ▸use the drug as time-limited support while behaviour is rebuilt, or when insomnia is severe and relief is needed quickly; ▸agree the duration in advance rather than extending it by default.
Summary
▸A different mechanism: orexin blockade instead of amplified inhibition. ▸Less morning grogginess thanks to a half-life of about 8 hours. ▸Proven sleep improvement at 25 and 50 mg; daytime functioning at 50 mg. ▸Dose usually 50 mg half an hour before bed, with at least 7 hours available; 25 mg at the clinician's discretion. ▸Not for narcolepsy; caution in apnoea and with alcohol. ▸Does not replace cognitive behavioural therapy, which remains first line.
Insomnia and the right approach can be discussed at a consultation; the product can be ordered here.
References
1. Mignot E, et al. Safety and efficacy of daridorexant in patients with insomnia disorder: results from two multicentre, randomised, double-blind, placebo-controlled, phase 3 trials. Lancet Neurol. 2022;21(2):125–139. PMID 35065036
2. QUVIVIQ (daridorexant) US Prescribing Information, Idorsia Pharmaceuticals.
3. QUVIVIQ (daridorexant) — Summary of Product Characteristics (EMA), Idorsia Pharmaceuticals.
Key facts
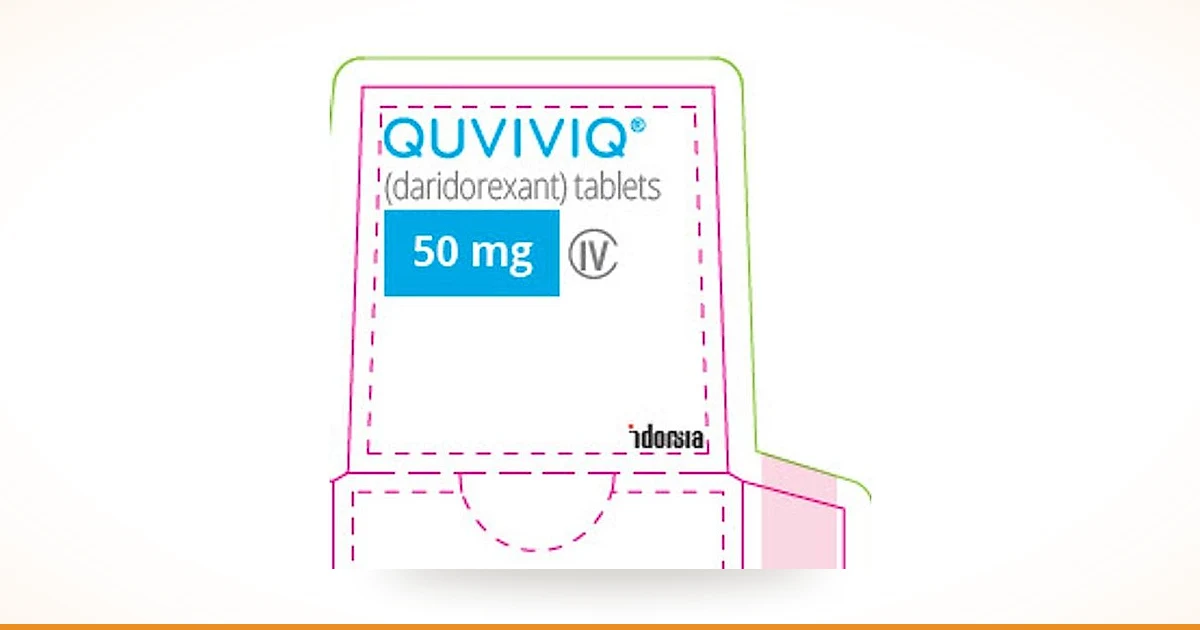
- Daridorexant (brand name Quviviq, Idorsia) is a dual orexin receptor antagonist (DORA class). It blocks not a "sleep centre" but the wakefulness system.
- Orexin (also called hypocretin) is a neuropeptide that holds the brain in a waking state. In narcolepsy the orexin neurons die and sleep becomes irresistible. Daridorexant switches that signal off temporarily and reversibly, approaching the physiology of falling asleep.
- The difference from zolpidem and benzodiazepines is fundamental: those amplify the inhibitory GABA system and suppress brain activity broadly. Hence their characteristic problems — morning grogginess, impaired coordination, falls, dependence.
- A half-life of about 8 hours is engineered so the drug covers the night and is largely cleared by morning — reducing residual sleepiness compared with long-acting hypnotics.
- Phase 3 trials (Lancet Neurology, 2022): versus placebo, daridorexant improved objective sleep measures — latency to sleep onset and wake after sleep onset — at 25 and 50 mg, and at 50 mg also self-reported daytime functioning.
- Dosing: 25 mg or 50 mg taken 30 minutes before bed, no more than once per night, and only with at least 7 hours available for sleep. The standard dose is 50 mg. 25 mg is used at the clinician's discretion, including in moderate hepatic impairment and with moderate CYP3A4 inhibitors (erythromycin, ciprofloxacin, ciclosporin). A fatty meal delays onset.
- The drug is a controlled substance in the US (Schedule IV), though its abuse potential is lower than that of classic hypnotics.
- The commonest adverse events are headache and daytime sleepiness. Rare class-specific phenomena include sleep paralysis, hypnagogic hallucinations and cataplexy-like episodes.
- Contraindicated in narcolepsy and with concomitant strong CYP3A4 inhibitors; caution with severe sleep-disordered breathing and with alcohol or other CNS depressants. Not recommended in severe hepatic impairment.
- Even with a new mechanism, cognitive behavioural therapy remains first line for chronic insomnia: its benefit persists after the course ends, whereas a drug works only while it is taken.