in pictures and a few words
What it is and why it matters
Sotatercept is an injection under the skin once every three weeks for adults with pulmonary arterial hypertension. This is a disease of the vessels that carry blood from the heart to the lungs.
- It is added to the medicines a person is already taking
- The first medicine for this disease that acts on the overgrowth of the vessel wall
What happens to the vessels
Cells in the wall of the lung vessels start to multiply too actively. The wall thickens, and the opening narrows.
- The right side of the heart finds it ever harder to push blood through — it gradually wears out
- Hence breathlessness on exertion, tiredness, fainting
- The disease is rare, but severe without treatment
How it differs from earlier medicines
Earlier medicines widen the vessel and relieve its spasm. This works and extends life, but the wall keeps overgrowing.
- Picture it: a pipe clogs up from inside, while its opening is adjusted from outside
- Sotatercept is the first to act on the overgrowth of the wall itself
How the trap works
In the vessel wall two signals compete: one holds cell growth back, the other spurs it on. In this disease the second one has the upper hand.
- The medicine catches surplus proteins in the blood that spur growth
- They do not reach the cells — and the upper hand goes back to the restraining signal
Fewer serious events at high risk
In adults at high risk, the injections were added to their main treatment. Death, lung transplant or a hospital stay due to worsening — counted together — happened much less often than with a dummy injection.
- Hospital stays due to worsening happened much less often
- The study was stopped early — the benefit turned out to be that clear
Tested in people. Tested in people: a study in adults at high risk, together with their main treatment.
They walk further
In adults who were already on stable main treatment, the distance walked in six minutes grew more with the injections than with a dummy injection.
- Almost all additional measures in this study also favoured the medicine
Tested in people. Tested in people: a study in adults who were already on main treatment.
How the injections are given
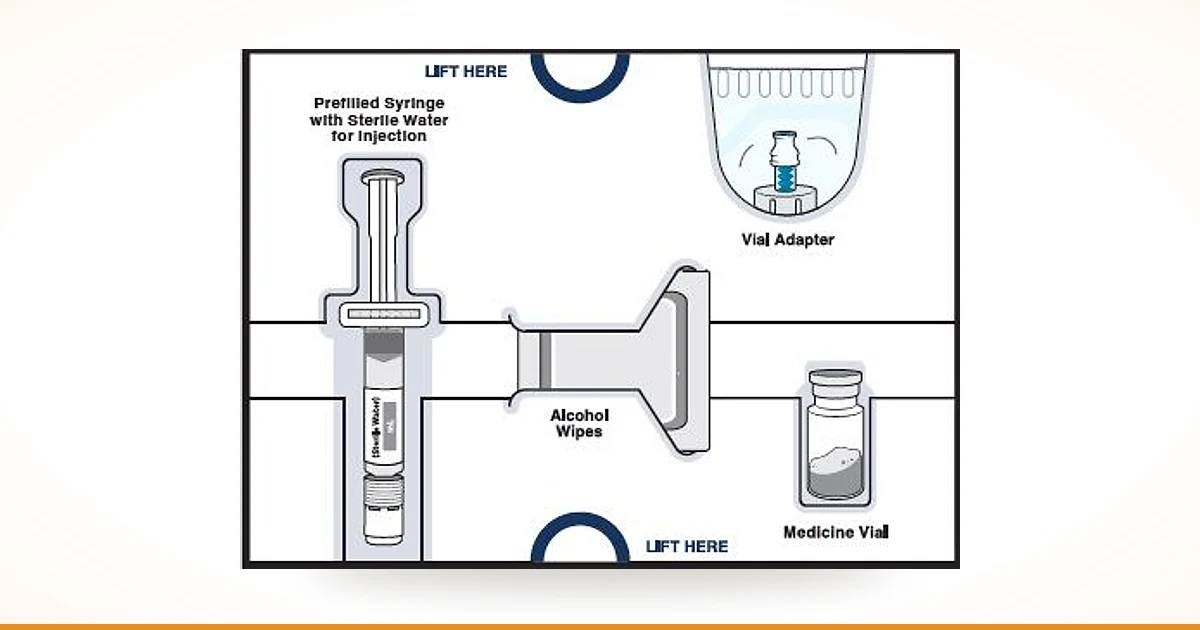
An injection under the skin once every three weeks — in addition to the main treatment, not instead of it.
- The usual treatment is not stopped when the injections start
- While the dose is being adjusted, blood is checked before every injection
- After that, blood tests are done regularly
What can happen and what is checked
Most often there are nosebleeds and widened small vessels on the skin and mucous membranes.
- The medicine raises haemoglobin, sometimes too much — so it is checked regularly
- Platelets — the cells that stop bleeding — may become fewer
- Both show up in a complete blood count
Important. Medicines of this group may affect the ability to have children. Discuss this with your doctor before treatment starts.
Who should see a doctor first
Discuss treatment with your doctor first if:
- you have pulmonary hypertension of another origin — the medicine is not designed for it
- your haemoglobin is already high or your platelets are low — this is decided separately and under monitoring
- you are planning a pregnancy — first discuss the effect on the ability to have children
Important. The injections are no reason to stop main treatment that works.
In one sentence
Sotatercept is the first injection for this disease that acts on the overgrowth of the vessel wall. In people at high risk on main treatment, serious events happened much less often with it.
- An injection once every three weeks; blood is checked regularly
Key points
Sotatercept (Winrevair) is a subcutaneous injection given once every three weeks to adults with pulmonary arterial hypertension (PAH), in addition to background therapy. It is the first drug to act not on spasm but on the growth of the vessel wall; it was approved by the FDA in March 2024.
| Situation | How it helps | What human studies showed |
|---|---|---|
| High-risk PAH, on maximum tolerated background therapy | fewer deaths, lung transplants or hospitalisations for worsening | ZENITH (NEJM, 2025), 172 patients: 17.4% versus 54.7% on placebo, hazard ratio 0.24 (95% CI 0.13–0.43; p<0.001) [2] |
| Hospitalisations (high risk) | fewer hospital admissions for worsening | ZENITH: 9.3% versus 50.0% on placebo [2] |
| PAH on stable background therapy | patients walk further in the six-minute walk test | STELLAR (NEJM, 2023), 323 patients: 40.8 m more than on placebo (95% CI 27.5–54.1; p<0.001); eight of nine secondary endpoints favoured the drug [1] |
How it helps
What happens in the pulmonary vessels
Pulmonary arterial hypertension is not high blood pressure in the familiar sense. It concerns the vessels carrying blood from the heart to the lungs.
Cells in the walls of those arteries begin to multiply excessively. The wall thickens, the lumen narrows, resistance to flow rises. The right ventricle must push blood through ever narrower vessels — and gradually wears out.
Clinically this is breathlessness on exertion, fatigue and fainting. The disease is rare, but untreated the outlook is poor.
How it differs from earlier drugs
The three classes on which treatment rested for decades — prostacyclins, endothelin receptor antagonists and phosphodiesterase-5 inhibitors — all essentially do one thing: widen the vessel by relieving spasm.
This works and prolongs life. But the wall keeps thickening regardless of whether the vessel is widened. Figuratively: the pipe furs up from inside while we adjust its bore from outside.
How the trap works
Two opposing signals meet in the cells of the vessel wall:
| Signal | What it does | What happens in the disease |
|---|---|---|
| Through the BMPR2 receptor | Restrains cell division | Weakened |
| Through activins and related proteins | Drives division | Amplified |
The balance tips toward growth, and the wall thickens. This is precisely why mutations in the BMPR2 gene are found in a substantial share of patients with the hereditary form.
Sotatercept is built as a fragment of the receptor fused to part of an antibody. It works as a trap: it captures surplus activins from the blood before they reach the cells. The advantage returns to the restraining signal.
Trials
▸ZENITH (NEJM, 2025) — 172 high-risk patients on the maximum tolerated background therapy. Events were counted rather than metres [2]:
| Event | Sotatercept | Placebo |
|---|---|---|
| Composite (death, lung transplantation or hospitalisation) | 17.4% | 54.7% |
| Death from any cause | 8.1% | 15.1% |
| Lung transplantation | 1.2% | 7.0% |
| Hospitalisation for worsening | 9.3% | 50.0% |
How it is given
| Parameter | Detail |
|---|---|
| Route | Subcutaneous injection |
| Frequency | Once every three weeks |
| Role in the regimen | Added to background therapy |
| Monitoring | Haemoglobin and platelets before every dose during titration |
| Discuss in advance | Fertility |
Who should see a doctor first
Side effects
▸Nosebleeds and telangiectasia — dilated small vessels on the skin and mucous membranes; the most characteristic events. ▸Rising haemoglobin: the blood thickens more than it should, so levels are monitored regularly. ▸Falling platelets — the same blood counts cover this. ▸Effects on fertility: drugs of this class may affect reproductive function, and that conversation belongs before treatment rather than after.
Who it is not for
▸Patients with pulmonary hypertension of another origin — the mechanism does not address them. ▸Anyone with an already high haemoglobin or low platelets — decided case by case and requiring monitoring. ▸Anyone planning pregnancy without discussing the fertility question with their doctor. ▸As a reason to stop background therapy that is working.
Bottom line
▸The first mechanism aimed at growth of the vessel wall rather than spasm. ▸ZENITH: events in 17.4% versus 54.7%; the trial was stopped early for efficacy. ▸Under regular monitoring — nosebleeds, telangiectasia, rising haemoglobin and falling platelets.
Treatment can be discussed at a consultation; the drug can be ordered here.
References
1. Hoeper MM, et al. Phase 3 Trial of Sotatercept for Treatment of Pulmonary Arterial Hypertension. N Engl J Med. 2023;388(16):1478–1490. PMID 36877098
2. Humbert M, et al. Sotatercept in Patients with Pulmonary Arterial Hypertension at High Risk for Death. N Engl J Med. 2025;392(20):1987–2000. PMID 40167274
3. WINREVAIR (sotatercept-csrk) — US Prescribing Information, Merck.
Caveats
What cannot be claimed yet:
▸That it replaces background therapy — in every trial it was added to it. ▸That the effect holds for years: ZENITH was stopped early, and long-term observation is still accumulating. ▸That it suits other forms of pulmonary hypertension — the indication covers the arterial form, not hypertension secondary to lung disease or thromboembolism. ▸How it ranks against other drugs in strength — no head-to-head trials have been run.
This material is for information only and does not replace a consultation with a doctor.
Key facts
- Sotatercept (brand name Winrevair, Merck) is a trap molecule that intercepts excess signalling proteins of the activin family; it was approved by the FDA in March 2024. It is the first drug in pulmonary arterial hypertension aimed not at widening the vessel but at the growth of its wall — that is, at the disease mechanism itself.
- In this disease the balance is disturbed: signalling through the BMPR2 receptor, which restrains growth of vascular cells, is weakened, while the opposing activin signal is amplified, so the wall thickens and the lumen narrows. Sotatercept binds the surplus activins and related proteins, returning the advantage to the restraining signal.
- STELLAR (NEJM, 2023): 323 patients on stable background therapy; six-minute walk distance improved by 40.8 m more than on placebo (95% CI 27.5–54.1; p<0.001).
- ZENITH (NEJM, 2025): 172 high-risk patients; a composite event — death, lung transplantation or hospitalisation — occurred in 17.4% versus 54.7% on placebo (hazard ratio 0.24; p<0.001), and hospitalisation for worsening disease in 9.3% versus 50.0%. The trial was stopped early: the interim analysis showed an advantage too clear to keep giving placebo.
- The drug is injected subcutaneously once every three weeks in addition to background therapy. The characteristic adverse events are nosebleeds and telangiectasia; the drug can raise haemoglobin and lower platelets, so these are checked before every dose during titration.