in pictures and a few words
What it is and why it matters
This number shows how well your cells hear insulin — the hormone that opens their door to sugar. It is calculated from two fasting blood tests.
- Blood sugar is the result; the index shows the cause
- The index changes, so you can see whether what you do is helping
- It is often not ordered: it isn’t part of routine check-ups
When cells hear insulin less well
The cell doors seem to jam: sugar has a harder time getting in. The pancreas responds by releasing more insulin and keeps blood sugar normal for a long time.
- When it can no longer keep up, blood sugar starts to rise in some people
- First to prediabetes, then to type 2 diabetes
Why blood sugar alone isn’t enough
Fasting sugar and the three-month average sugar test rise late. For years insulin can be above normal while both of these tests are still normal.
- During this time a person usually knows nothing about it
- The index can spot insulin resistance before blood sugar rises
How to test and calculate
In the morning, strictly fasting — 8–12 hours without food — take two tests at the same time: insulin and sugar (glucose). Results are usually ready in 1–2 days.
- Sugar in mmol/L: insulin × sugar ÷ 22.5
- Sugar in mg/dL: insulin × sugar ÷ 405
- Insulin is used in μIU/mL; if it is in pmol/L, divide it by 6 first
What is normal
There is no single normal value: different countries arrived at different cut-offs. In practice, 2.5 is the most common guide.
- One result is not a diagnosis, and a small difference does not mean disease
- Your lab sets the normal range for insulin — check your report
- Retest at the same lab and watch how the number changes
What else the index tells you
Insulin resistance lies behind many conditions. One test helps you see their common root.
- Extra weight, especially around the belly, and high blood pressure
- Changes in blood fats, fat in the liver, polycystic ovaries in women
- A higher risk of heart attack and stroke
Lowering the index: food and supplements
The index is reversible: it can come down when food, movement and sleep change. You can start with food.
- Fewer refined carbs, more protein and healthy fats
- All meals within 8–10 hours of the day
- Supplements: berberine 900–1500 mg a day, magnesium 200–400 mg, chromium 500 mcg, omega-3 2–4 g
Movement and sleep
Muscles are the biggest users of sugar in the body. Movement and sleep also lower the index.
- A 15–20 minute walk after meals
- Strength training 2–3 times a week
- 7–8 hours of sleep in the dark: even after one short night, cells heard insulin less well
Who should see a doctor first
An index above 2.5 is a reason for further tests, even if blood sugar is normal. Don’t wait for blood sugar to rise.
- One result is not a diagnosis: retest fasting insulin and sugar at the same lab
- Other tests show the bigger picture: blood fats, liver, inflammation, vitamin D, magnesium
- Pregnant, breastfeeding or on regular medication — berberine only with your doctor
Important. No diabetes, but blood sugar is repeatedly below 3.0 mmol/L (54 mg/dL) or above 8.9 mmol/L (160 mg/dL) — see a doctor.
In one sentence
Blood sugar rises late, while the index from fasting insulin and sugar shows the cause earlier — and it shows whether food, movement and sleep are helping.
The Most Important Test Nobody Orders
In 15 years of clinical practice, I've treated over 500 patients with type 2 diabetes and prediabetes. Nearly every one tells the same story: years of endocrinologist visits, fasting glucose tests, HbA1c checks, metformin prescriptions.
This is like diagnosing heart failure without measuring blood pressure. Blood sugar is a consequence. HOMA-IR reveals the cause: how much your cells resist insulin. And that determines whether the disease can be reversed.
What Is Insulin Resistance
Insulin resistance is a condition in which the body's cells respond less to insulin. Insulin is the key hormone that "opens the doors" of cells for glucose.
With insulin resistance, those doors get stuck: at the same insulin level, less glucose gets into cells. The pancreas responds by producing more insulin to "push" glucose in, and for a long time this keeps blood sugar normal. When this compensation can no longer keep up, blood sugar starts to rise in some people — first to prediabetes, then to type 2 diabetes.
One hypothesis is that persistently high insulin itself further reduces cell sensitivity and closes the loop: more insulin, more resistance, even more insulin. Which comes first — hyperinsulinemia or resistance — is still debated (Shanik MH, Diabetes Care 2008).
What Is HOMA-IR and How Is It Calculated
HOMA-IR (Homeostatic Model Assessment of Insulin Resistance) is a mathematical model developed at Oxford University in 1985. The formula is simple:
HOMA-IR = (fasting insulin × fasting glucose) / 22.5
Insulin is measured in μIU/mL, glucose in mmol/L. If glucose is in mg/dL, the formula becomes: (insulin × glucose) / 405. If insulin is reported in pmol/L, divide it by 6 first.
You need just two tests drawn at the same blood draw, taken in the morning after an overnight fast: insulin and glucose. Cost: typically $15-30 at most labs. Results within 1-2 days.
What Is a Normal HOMA-IR
There is no single normal value. HOMA-IR is a calculated (surrogate) index; the reference method for measuring insulin sensitivity is the clamp (Muniyappa R, Am J Physiol Endocrinol Metab 2008). In the Matthews model, 1.0 corresponds to young, healthy, normal-weight adults, and a single estimate is imprecise: its coefficient of variation is about 31% (Matthews DR, Diabetologia 1985). So the difference between 2.3 and 2.7 does not mark a move from health to disease.
Insulin resistance thresholds come from different populations and different methods, and they do not agree:
- 2.4 — upper reference limit in healthy Japanese adults; the authors consider values from 2.5 up a sign of insulin resistance (Yamada C, J Diabetes Investig 2011)
- 2.77 — lower limit of the top quintile in people without obesity or metabolic disorders, Bruneck, Italy (Bonora E, Diabetes 1998)
- 2.7 — 90th percentile in healthy participants, Brazil (Geloneze B, Arq Bras Endocrinol Metabol 2009)
- 3.46 — 90th percentile in the general adult population, Spain (Gayoso-Diz P, BMC Endocr Disord 2013)
- 3.8 — cut-off in adult Americans of Mexican descent, derived with machine-learning methods (Qu HQ, PLoS One 2011)
If the threshold is chosen by how well it detects metabolic syndrome, it is lower: 1.7 in Japanese adults without diabetes (Yamada C, J Diabetes Investig 2012), 2.05 in Spain and 2.3 in Brazil (the same studies as above). In practice, a cut-off of about 2.5 is used most often. In the range of roughly 1.7–2.5, some people already have components of metabolic syndrome.
There is no single normal value for fasting insulin either: the reference range is set by each laboratory for its own assay. On the same samples, 11 commercial assays differed by up to a factor of two (Manley SE, Clin Chem 2007). In an American Diabetes Association workgroup evaluation, the among-assay coefficient of variation was 12–66% (median 24%), and a common reference preparation did not reduce it (Marcovina S, Clin Chem 2007). For orientation: in a small sample of 65 healthy adults from Valencia, the insulin resistance cut-off at the 75th percentile corresponded to a fasting insulin of 12 μIU/mL (72 pmol/L) (Ascaso JF, Diabetes Care 2003). Judge your result against your own laboratory's reference range.
That is why HOMA-IR itself depends on the laboratory. The model's authors cite cohort and epidemiological studies as examples of its appropriate use (Wallace TM, Diabetes Care 2004); for an individual, results are best compared over time and in the same laboratory.
Why HbA1c Is Not Enough
HbA1c is the standard marker for diabetes management. It reflects average blood sugar over 3 months. The problem: HbA1c rises late in the disease process.
Here's the typical timeline of type 2 diabetes development:
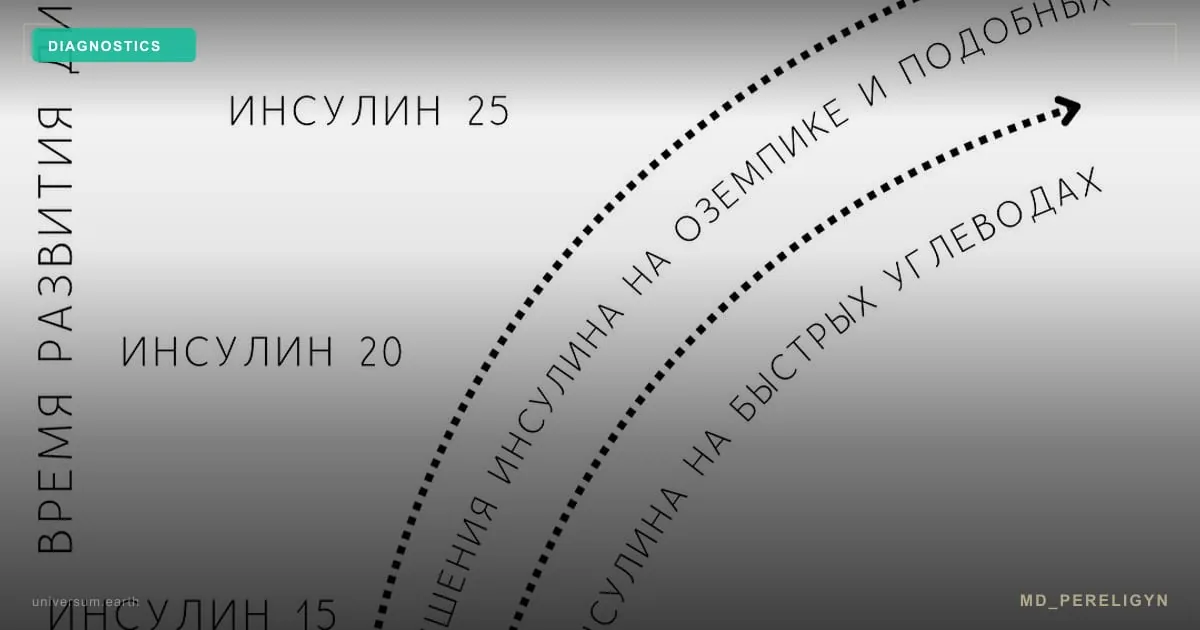
Years 0-5: Insulin resistance builds. HOMA-IR gradually rises past the population thresholds (2.4–3.8). Fasting insulin is above the laboratory reference range. Fasting glucose is normal. HbA1c is normal. The patient knows nothing.
Years 5-8: HOMA-IR is usually above the population thresholds (2.4–3.8). Fasting glucose starts rising: 100–125 mg/dL (5.6–6.9 mmol/L). HbA1c hits 5.7-6.4% — prediabetes. Doctor says: "Lose weight, come back in six months."
Year 8+: The pancreas becomes exhausted. Insulin production falls. Glucose 126 mg/dL (7.0 mmol/L) or higher. HbA1c 6.5% or higher. Diagnosis: type 2 diabetes. Metformin prescribed.
See the problem? HOMA-IR could have caught the disease at stage one — 5-8 years before diagnosis. But no one ordered it.
Why Doctors Don't Order HOMA-IR
There are several reasons, and they're systemic:
3. No drug "for HOMA-IR." If a doctor finds elevated HOMA-IR, what do they prescribe? There's no standard pharmaceutical response. Metformin partially reduces resistance but doesn't eliminate it — see the head-to-head comparison of berberine vs metformin for a closer look at the trade-offs. A comprehensive approach — nutrition, supplements, lifestyle — is needed. Most endocrinologists lack the time and expertise for this.
What HOMA-IR Tells You About Your Health
HOMA-IR isn't just a diabetes marker. Insulin resistance underlies a whole spectrum of conditions:
- Obesity, especially abdominal (visceral fat)
- Hypertension — insulin promotes sodium retention, raising blood pressure
- Dyslipidemia — high triglycerides, low HDL
- Fatty liver disease (NAFLD) — affects up to 70% of people with insulin resistance
- Polycystic ovary syndrome (PCOS) — insulin resistance is found in 70-80% of women with PCOS
- Increased cardiovascular risk — insulin resistance is an independent risk factor for heart attack and stroke
One test — and you see the root cause behind a dozen different diagnoses.
Clinical Case: Andrew, 47 Years Old
Andrew came to me complaining of fatigue and weight gain (+26 lbs over 2 years). His GP said: "Your labs are normal, just eat less."
The "normal" results: fasting glucose 95 mg/dL (5.3 mmol/L), HbA1c 5.5%. Technically, within range.
I ordered an expanded panel:
- Fasting insulin: 22.4 μIU/mL (134 pmol/L) (above the laboratory reference range)
- HOMA-IR: 5.3 (above every population threshold, 2.4–3.8)
- C-peptide: 4.1 ng/mL (upper range)
- Triglycerides: 248 mg/dL (2.8 mmol/L) (elevated)
- ALT: 52 U/L (elevated — sign of fatty liver)
The picture was clear: significant insulin resistance with compensatory hyperinsulinemia. His pancreas was producing far more insulin than usual to keep blood sugar normal. Without intervention — diabetes within 2-3 years.
After 4 months on the md_pereligyn protocol: HOMA-IR dropped to 1.8, insulin to 7.2 μIU/mL (43 pmol/L), weight decreased by 24 lbs, ALT normalized. Andrew avoided the diabetes that "normal" tests couldn't see.
How to Check Your HOMA-IR
The process is straightforward:
Can You Lower HOMA-IR
Yes — and this is the greatest value of this index: it's reversible and changes over time, so it shows whether correction is working.
What works to lower HOMA-IR:
Nutrition: reduce refined carbohydrates, increase protein and healthy fats, eat within an 8-10 hour window.
Targeted supplements: berberine (900-1500 mg/day), magnesium glycinate (200-400 mg), chromium picolinate (500 mcg), omega-3 (2-4 g). All have evidence for reducing HOMA-IR — see the full evidence review of the best supplements for insulin resistance for dosing and study data.
Physical activity: walking after meals (15-20 min), resistance training 2-3 times per week. Muscle mass is the body's largest glucose consumer.
Sleep: 7-8 hours in darkness. A single night of only 4 hours of sleep reduced insulin sensitivity by about 20-25% (9 healthy volunteers; Donga et al., 2010, Journal of Clinical Endocrinology & Metabolism, PMID: 20371664[14]).
Who should see a doctor first
No diabetes, but blood glucose repeatedly below 3.0 mmol/L (54 mg/dL) or above 8.9 mmol/L (160 mg/dL) — see a doctor.
Pregnant, breastfeeding or on regular medication — take berberine only after talking to your doctor.
Your First Step
Order a fasting insulin test. It's one inexpensive test that can change your life. If your HOMA-IR is above 2.5 — the cut-off used most often in practice (population thresholds range from 2.4 to 3.8) — don't wait for blood sugar to climb and for a diabetes diagnosis. Act now, while the condition is reversible.
During a consultation, we'll review your labs, assess your insulin resistance over time, and create a personalized correction plan.
References
- Shanik MH, Diabetes Care 2008. PMID 18227495
- Muniyappa R, Am J Physiol Endocrinol Metab 2008. PMID 17957034
- Matthews DR, Diabetologia 1985. PMID 3899825
- Yamada C, J Diabetes Investig 2011. PMID 24843516
- Bonora E, Diabetes 1998. PMID 9753305
- Geloneze B, Arq Bras Endocrinol Metabol 2009. PMID 19466221
- Gayoso-Diz P, BMC Endocr Disord 2013. PMID 24131857
- Qu HQ, PLoS One 2011. PMID 21695082
- Yamada C, J Diabetes Investig 2012. PMID 24843594
- Manley SE, Clin Chem 2007. PMID 17363420
- Marcovina S, Clin Chem 2007. PMID 17272483
- Ascaso JF, Diabetes Care 2003. PMID 14633821
- Wallace TM, Diabetes Care 2004. PMID 15161807
- PMID 20371664
Key facts
- HOMA-IR = (fasting insulin × fasting glucose) / 22.5; if glucose is in mg/dL, divide by 405.
- There is no single normal HOMA-IR: insulin resistance thresholds in studies from Japan, Italy, Brazil, Spain and the US range from 2.4 to 3.8; about 2.5 is used most often in practice, and a single value is not a diagnosis.
- HOMA-IR was developed at Oxford University in 1985 and needs only fasting insulin and glucose.
- A single night of sleep deprivation reduces insulin sensitivity by about 20-25% (Donga et al., 2010).
- Fatty liver disease (NAFLD) affects up to 70% of people with insulin resistance; PCOS 70-80% of women.