in pictures and a few words
What it is and why it matters
ApoB is a blood test that counts the particles carrying cholesterol. It shows heart attack risk more accurately than the familiar “bad” cholesterol.
- Available in most large labs, costs about as much as a regular cholesterol test
- Especially useful when cholesterol is “normal” but risk is higher than usual
- Test it with the “good” cholesterol protein: their ratio predicts heart attack well
Particle count, not weight
Cholesterol travels in the blood inside particles. Each one carries exactly one ApoB protein — so the test counts the particles themselves.
- The usual “bad” cholesterol test shows how much cholesterol is inside the particles
- ApoB shows how many particles there are
- Plaque is built not by cholesterol mass but by particles that get into the vessel wall
When “normal” is misleading
Sometimes “bad” cholesterol is normal while ApoB is high. This happens when particles are small: each holds little cholesterol, but there are many of them.
- The usual test sees little cholesterol and shows “normal”
- ApoB sees that there are actually many particles
- This often happens with metabolic syndrome, type 2 diabetes and excess weight
Who should get tested
At least once — anyone whose risk of heart and blood vessel disease is higher than usual. Especially if cholesterol is “normal”.
- Metabolic syndrome, type 2 diabetes or excess weight
- Low “good” cholesterol together with high triglycerides
- Early heart attack in relatives with “normal” cholesterol
Which number is the target
The higher the risk, the lower the target. Lab reports use mg/dL or g/L: 100 mg/dL is 1.0 g/L.
- Moderate risk — below 100 mg/dL (1.0 g/L)
- Diabetes for over 10 years or inherited high cholesterol — below 80 mg/dL (0.8 g/L)
- After a heart attack, stroke, stent or bypass — below 65 mg/dL (0.65 g/L)
Food against extra particles
A Mediterranean diet lowers ApoB: olive oil, fish, vegetables, nuts, legumes.
- Less fatty meat, hard cheese, palm and coconut oil
- Less fast food, store-bought pastries and margarine: these fats raise ApoB the most
- Less sugar; more oats and legumes — their fiber helps clear particles from the blood
Movement, sleep, alcohol
There are fewer small particles when the body responds well to insulin — the hormone that clears sugar from the blood. Without this, ApoB doesn’t return to normal.
- Strength training 2–3 times a week and 150 minutes of cardio a week
- Sleep 7–9 hours: with under 6 hours of sleep, the liver makes more of these particles
- Alcohol — under 14 g a day for men and under 7 g for women
Medicines and supplements
At low and intermediate risk, ApoB is lowered by diet, exercise and supplements — bergamot, berberine, red yeast rice. At high risk, statins still come first.
- Statins lower “bad” cholesterol more than ApoB: leftover risk shows only in ApoB
- Treatment is checked by ApoB: retest after starting or changing the dose, then regularly
- If the target isn’t reached, the doctor may add another medicine
Who should see a doctor first
Supplements and any changes to treatment — only after talking to your doctor. Especially in these cases.
- After heart attack or stroke, with type 2 diabetes — statins first, supplements just help
- Keto diet: in some people ApoB rises sharply — retest it 3 months after starting
- Before hormones — testosterone or estrogens — get ApoB tested first
Important. Don’t stop cholesterol medicines or change the dose on your own. Red yeast rice is not taken together with them.
In one sentence
What matters is not how much cholesterol is in the particles but how many particles there are. ApoB counts them: if your risk is above usual, get tested and discuss the target with your doctor.
Introduction: why ApoB is more accurate than LDL
For the past thirty years, the standard lipid panel has been built around LDL cholesterol. But LDL measures the mass of cholesterol inside atherogenic particles, not the number of the particles themselves. This is a fundamental distinction, and it explains why a patient with “normal” LDL can still have a myocardial infarction.
Apolipoprotein B-100 (ApoB) is a structural protein present in exactly one copy on each atherogenic particle: LDL, VLDL, IDL, Lp(a), and chylomicron remnants. By measuring ApoB, we obtain a direct count of all atherogenic particles in plasma.
In other words: ApoB is the roll call of infantry before an assault. LDL is the total weight of their equipment. The defense is breached by numbers, not by mass.
🌀
What the discordance pattern means
When LDL and ApoB are concordant, both markers show the same risk picture. But in a substantial proportion of patients, discordance occurs: LDL appears “normal” while ApoB is high, or the reverse.
Mechanism of discordance: in metabolic dysfunction, small dense LDL (sdLDL) predominates. Each particle contains little cholesterol, but the number of particles is high. The standard lipid panel, which measures cholesterol mass, sees a “normal” result. ApoB sees the real number of atherogenic particles.
▸Large buoyant LDL (lbLDL) — more cholesterol per particle, fewer particles. LDL is high, ApoB is moderate. ▸Small dense LDL (sdLDL) — less cholesterol per particle, many particles. LDL is “normal”, ApoB is high. ▸Triglyceride-rich remnants — add ApoB beyond the LDL fraction; patients with high TG have systemically higher ApoB at the same LDL level.
The discordance pattern occurs in 30–50% of patients with metabolic syndrome, type 2 diabetes, obesity, low HDL, and high triglycerides. These are exactly the patients in whom the standard lipid panel provides false reassurance.
🌀
When ApoB and LDL diverge: 4 scenarios
Four clinical situations in which ApoB is mandatory:
•Metabolic syndrome, obesity, insulin resistance — sdLDL predominates, and ApoB is substantially higher than predicted from LDL. The risk of coronary artery disease is underestimated by the standard lipid panel. •Type 2 diabetes (T2D) — a combination of sdLDL + triglyceride-rich remnants. ApoB is often 20–30% higher than it “should be” based on LDL. This is a key scenario for missed risk in primary prevention. •Familial combined hyperlipidemia (FCHL) — many particles with normal or moderately elevated LDL. A family history of early myocardial infarction despite “normal” lipids is a reason to order ApoB. •After statin initiation — statins lower LDL more than ApoB. Residual risk is visible only through ApoB. Patients with “achieved LDL <70” may still have ApoB 90+ and ongoing progression of atherosclerosis.
In each of these scenarios, LDL-guided treatment creates a false sense of control. The real residual risk is determined only by ApoB.
🌀
ApoB target levels
ApoB targets by risk category (ESC/EAS 2019):
| Risk category | ApoB target |
|---|---|
| Moderate | <100 mg/dL (<1.0 g/L) |
| High | <80 mg/dL (<0.8 g/L) |
| Very high | <65 mg/dL (<0.65 g/L) |
▸Moderate risk (young people with diabetes <10 years, no other risk factors): <100 mg/dL ▸High risk (FH without other risk factors, diabetes ≥10 years without target-organ damage, eGFR 30–59): <80 mg/dL ▸Very high risk (after MI, stroke, revascularization; diabetes with target-organ damage; eGFR <30): <65 mg/dL
Conversion to SI units: 1 mg/dL = 0.01 g/L. That is, <65 mg/dL = <0.65 g/L.
These thresholds are stricter than familiar “LDL targets” precisely because ApoB directly measures particle number and leaves no room for discordance-related misclassification.
🌀
Markers to test together with ApoB
ApoB does not exist in isolation. To build a complete picture of vascular risk, it is combined with:
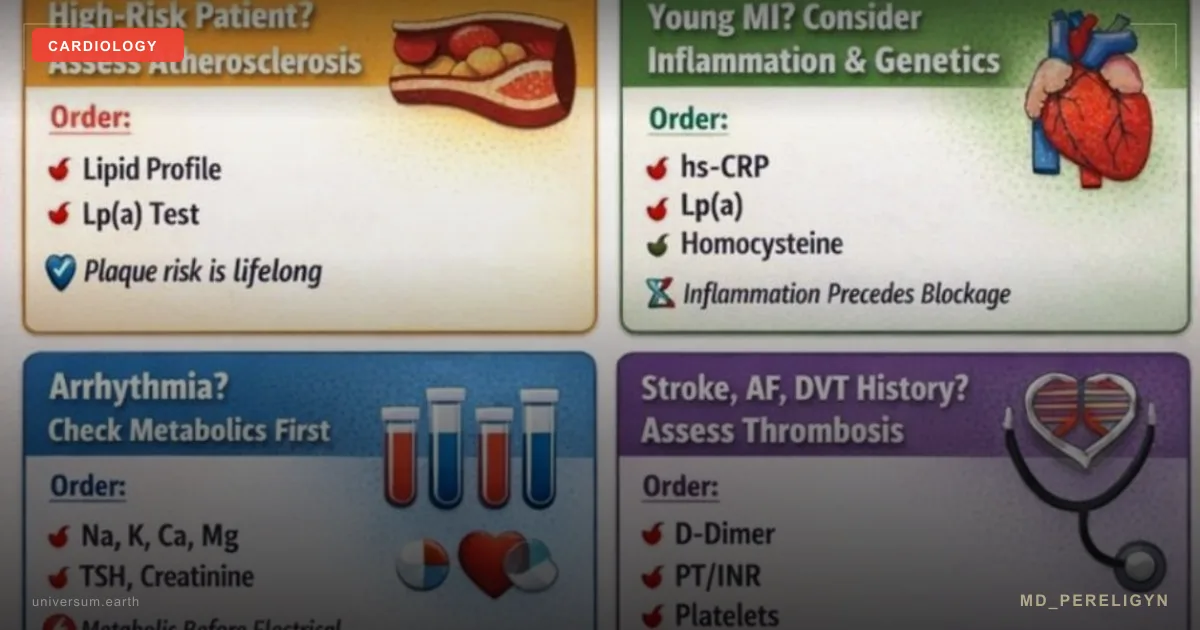
▸ApoA1 — the structural protein of HDL. The ApoB / ApoA1 ratio is one of the best single predictors of myocardial infarction (INTERHEART study, Walldius G, J Intern Med 2004, PMID 14746556). Target <0.7 in men, <0.6 in women. ▸Lp(a) — a genetic factor, independent of lifestyle, measured once. Levels >50 mg/dL double cardiovascular risk; >180 mg/dL increases it sixfold. ▸hsCRP — a marker of vascular inflammation that complements ApoB. >2 mg/L on repeated tests indicates high risk. ▸Fasting triglycerides — an indicator of residual particles, remnants, and sdLDL. ▸TG / HDL ratio — a surrogate marker of insulin resistance and sdLDL predominance. Target <2 (mg/dL) or <0.87 (mmol/L). ▸Advanced lipid panel with sdLDL and oxLDL — atherogenic subfractions that penetrate the subendothelial space. ▸Homocysteine — a cofactor of endothelial injury. Target <8 μmol/L.
A detailed interpretation of these markers is provided in the article Endothelium: the foundation of vascular health.
🌀
Holistic protocol for lowering ApoB
Principle of the md_pereligyn protocol: lowering ApoB is not only about statins. It means working with particle production in the liver, their clearance through LDL receptors, and the oxidative environment in plasma.
1. Foundational diet
▸Mediterranean / DASH pattern — olive oil, fish, vegetables, nuts, legumes. ApoB reduction by 10–15% over 12 weeks. ▸Limit saturated fat to <7% of calories — palm and coconut oil, fatty beef, hard cheeses. ▸Limit trans fats — industrial baked goods, fast food, margarines. Trans fats increase ApoB more strongly than any other fat category. ▸Limit rapidly absorbed carbohydrates and fructose — hepatic fructose directly increases VLDL and triglyceride production, overloading the system with ApoB-containing particles. ▸Soluble fiber 10–25 g/day — oats, psyllium, legumes. Binds bile acids and increases LDL receptor expression.
2. Targeted nutraceuticals
▸Bergamot (citrus extract) 500–1000 mg/day — ApoB reduction by 15–20% over 12 weeks in double-blind studies. Activates AMPK, reduces HMG-CoA reductase activity, and increases LDL receptors. ▸Berberine 500 mg 2–3 times/day — increases LDL receptor expression via the ERK pathway. Reduces LDL and ApoB by 20–25%. Take with meals. ▸Red yeast rice (monacolins) — a natural HMG-CoA reductase inhibitor. In the EU a daily portion must provide less than 3 mg of monacolins (Regulation (EU) 2022/860). Monacolin K is structurally identical to the active substance of one of the statins, so it is not combined with statins; discuss use with your doctor. ▸Plant sterols 2 g/day — compete with cholesterol for intestinal absorption. Reduce LDL and ApoB by 6–10%. ▸Omega-3 (EPA+DHA) 2–4 g/day — reduce triglycerides and remnants; at high doses, may reduce ApoB. ▸Niacin (nicotinic acid) 500–1500 mg/day — reduces Lp(a) by 25% and ApoB by 15%. Use cautiously in insulin resistance.
3. Support insulin sensitivity
sdLDL is a consequence of insulin resistance. Without addressing the metabolic foundation, ApoB will not normalize.
▸Magnesium (glycinate / taurate) 400 mg/day — improves insulin sensitivity. ▸Chromium picolinate 200 μg/day — potentiates insulin signaling. ▸Alpha-lipoic acid 600 mg/day — antioxidant; improves insulin sensitivity. ▸Resistance training 2–3 times/week — increases muscle mass, the main “consumer” of glucose. ▸Aerobic exercise 150 min/week — reduces visceral fat, a key source of inflammatory cytokines.
4. Sleep and stress
▸Sleep 7–9 hours — less than 6 hours increases cortisol and stimulates hepatic VLDL production. ▸Stress management — meditation, breathing practices; chronic stress raises ApoB through cortisol. ▸Alcohol <14 g/day in men, <7 g/day in women — ethanol stimulates triglyceride and VLDL synthesis.
5. Pharmacotherapy
Statins and ezetimibe remain the standard of care in high and very high risk. Treatment monitoring should be based on ApoB, not LDL.
▸Rosuvastatin 5–20 mg or atorvastatin 10–40 mg — reduces ApoB by 30–45%. ▸Ezetimibe 10 mg — added when the target is not achieved; additional −15% ApoB. ▸PCSK9 inhibitors (evolocumab, alirocumab) — for familial hypercholesterolemia and high residual risk; reduce ApoB by 50%+. ▸Bempedoic acid — for patients with statin intolerance.
🌀
What does NOT work (and why)
▸Monitoring only LDL in a patient with metabolic syndrome — misses discordance; residual risk is visible only through ApoB. ▸“Normal” LDL without ApoB testing in a patient with type 2 diabetes — a false sense of control. ApoB should be measured in all patients with T2D. ▸Isolated dietary cholesterol reduction without improving insulin sensitivity — sdLDL remains, and ApoB does not normalize. ▸High doses of omega-6 oils (sunflower, corn oil) — lower LDL but increase oxidative stress and may increase the proportion of oxidized particles. ▸Low-carbohydrate ketogenic diet without ApoB monitoring — in some patients (“hyper-responders”), ApoB rises sharply on keto; testing 3 months after initiation is mandatory. ▸No check after starting or changing the dose — check ApoB 8 ± 4 weeks after initiation or adjustment, then annually once at target.
🌀
When to order ApoB
▸Any patient with CVD risk above the population baseline — once for baseline assessment ▸Suspected discordance: metabolic syndrome, type 2 diabetes, obesity, low HDL + high triglycerides ▸Family history of early myocardial infarction despite “normal” lipids ▸Monitoring statin and ezetimibe therapy — 8 ± 4 weeks after initiation or dose change, annually once at target ▸Decision-making about PCSK9 inhibitor therapy ▸Ketogenic or low-carbohydrate diet — check 3 months after initiation ▸Before starting hormone therapy (testosterone, estrogens) — baseline assessment
I perform a complete vascular risk assessment (ApoB, ApoA1, Lp(a), advanced lipid panel with sdLDL, hsCRP, omega-3 index) and develop a personalized ApoB-lowering protocol.
🌀
Conclusion
ApoB is displacing LDL and non-HDL as the primary metric of atherogenic risk in updated ESC (2019), AACE (2020), and NLA (2020) recommendations. This did not happen because LDL “does not work”, but because in every second patient with metabolic syndrome or diabetes, LDL and ApoB are discordant, and LDL underestimates true risk.
The principle is simple: when discordance is present, manage ApoB, not LDL. The targets are stricter — but they provide an honest picture of how many atherogenic particles attack your endothelium every day.
Treat the number of particles, not their weight.
🌀
Sources
▸Sniderman AD, Thanassoulis G, Glavinovic T, et al. Apolipoprotein B particles and cardiovascular disease: a narrative review. JAMA Cardiol 2019;4:1287–1295. PMID 31642874 ▸Walldius G, Jungner I. Apolipoprotein B and apolipoprotein A-I: risk indicators of coronary heart disease and targets for lipid-modifying therapy. J Intern Med 2004;255:188–205. PMID 14746556 ▸Mach F, Baigent C, Catapano AL, et al. 2019 ESC/EAS Guidelines for the management of dyslipidaemias. Eur Heart J 2020;41:111–188. PMID 31504418
Related articles: Endothelium: the foundation of vascular health, Cholesterol without statins.
🌀
FAQ
If my LDL is normal, do I need to test ApoB at all? Yes, especially if metabolic syndrome, type 2 diabetes, obesity, low HDL, or a family history of early myocardial infarction is present. In 30–50% of such patients, LDL is “normal” while ApoB is high. This is the discordance pattern, and it determines real risk.
Can ApoB be tested in any laboratory? Yes. ApoB is an immunoturbidimetric assay available in most large commercial laboratories. Its cost is comparable to a standard lipid panel. I recommend ordering it together with ApoA1 to calculate the ApoB / ApoA1 ratio.
How many times per year should ApoB be monitored while taking statins? First check 8 ± 4 weeks after starting or adjusting therapy, repeated at that interval until the target is reached; once at target — annually, more often if adherence or tolerability is a problem.
Can ApoB be lowered without statins? Yes. In low and intermediate risk, foundational diet + bergamot / berberine / red yeast rice + improvement in insulin sensitivity can reduce ApoB by 20–30% over 3 months. In high and very high risk, statins remain first-line therapy, but the protocol enhances their effect. Red yeast rice is not combined with statins.
Which is more important: ApoB or Lp(a)? Both are important; they measure different things. ApoB is the total number of atherogenic particles, which can be modified through diet, nutraceuticals, and statins. Lp(a) is a genetic factor, 90% determined by heredity; lifestyle has almost no effect on it, but it requires stricter ApoB targets. Lp(a) is measured once, while ApoB is measured periodically.
This article is for informational purposes only and is not a substitute for professional medical advice. Discuss any nutraceutical, medication adjustment, or diagnostic procedure with your treating physician before starting.
Key facts
- ApoB is present in exactly one copy on each atherogenic particle, giving a direct count of all particles in plasma.
- The discordance pattern — LDL and ApoB diverging — occurs in 30–50% of patients with metabolic syndrome or type 2 diabetes.
- ESC/EAS 2019 ApoB targets: <100 mg/dL (1.0 g/L) at moderate risk, <80 (0.8 g/L) at high, <65 (0.65 g/L) at very high risk, including after MI.
- The ApoB / ApoA1 ratio is one of the best single predictors of myocardial infarction (INTERHEART study).
- Statins lower LDL more than ApoB, so residual risk is visible only through ApoB.